




To compare the efficacy and safety of prolonged prone positioning (PPP; ≥24 h continuous proning) versus conventional prone positioning (CPP; daily sessions < 24 h) in patients with acute respiratory distress syndrome (ARDS).
DesignSystematic review and meta-analysis of randomized controlled trials (RCTs) and non-randomized studies (NRSs).
SettingStudies retrieved from a manual search, Embase, PubMed, and Scopus from inception up to February 2026.
Patients or participantsAdult patients with ARDS receiving prone positioning. RCTs and NRSs at non-critical risk of bias comparing PPP versus CPP were included.
InterventionsPPP versus CPP strategies.
Main variables of interestShort-term mortality, intensive care unit (ICU) length of stay, duration of mechanical ventilation, pressure injuries, endotracheal tube dislodgement, loss of vascular access, and edema.
ResultsNine studies (five RCTs and four NRSs) including 2624 patients, mostly with COVID-19-related ARDS, were analyzed. PPP was associated with lower short-term mortality compared with CPP (RR 0.75, 95% CI 0.58–0.97). However, in a sensitivity analysis restricted to RCTs and low-risk NRSs, the mortality benefit was no longer observed (RR 0.94, 95% CI 0.79–1.13). ICU length of stay, duration of mechanical ventilation, and most safety outcomes were similar between groups, although PPP may slightly increase pressure injuries and edema. The certainty of evidence was low across all outcomes.
ConclusionsPPP may reduce short-term mortality without a clear increase in serious adverse events. However, further high-quality RCTs, particularly in patients with non-COVID-19 associated ARDS, are needed to confirm these findings.
Comparar la eficacia y seguridad del posicionamiento prono prolongado (PPP; ≥24 h continuas) frente al posicionamiento prono convencional (PPC; sesiones diarias de < 24 h) en pacientes con síndrome de distrés respiratorio agudo (SDRA).
DiseñoRevisión sistemática y metaanálisis de ensayos clínicos aleatorizados (ECA) y estudios no aleatorizados (ENA).
ÁmbitoBúsqueda manual además de Embase, PubMed y Scopus desde su inicio hasta febrero de 2026.
Pacientes o participantesPacientes adultos con SDRA sometidos a posicionamiento prono. Se incluyeron ECA y ENA con riesgo de sesgo no crítico que compararan PPP versus PPC.
IntervencionesEstrategias de PPP versus PPC.
Variables de interés principalesMortalidad a corto plazo, estancia en UCI, duración de ventilación mecánica y eventos adversos.
ResultadosSe incluyeron nueve estudios (cinco ECA y cuatro ENA) con 2.624 pacientes, mayoritariamente con SDRA debido a COVID-19. El PPP se asoció con menor mortalidad a corto plazo (RR 0,75; IC 95% 0,58–0,97). Sin embargo, este efecto desapareció en análisis restringidos a ECA y ENA de bajo riesgo (RR 0,94; IC 95% 0,79–1,13). La estancia en UCI, la duración de la ventilación mecánica y la mayoría de los eventos adversos fueron similares, aunque el PPP podría aumentar levemente las lesiones por presión y el edema. La certeza de la evidencia fue baja para todos los desenlaces.
ConclusionesEl PPP podría reducir la mortalidad a corto plazo sin un aumento claro de eventos adversos graves. Sin embargo, se requieren ECA de alta calidad, especialmente en pacientes con SDRA no asociado a COVID-19, para confirmar estos hallazgos.
Acute respiratory distress syndrome (ARDS) is associated with significant morbidity and mortality, with hospital mortality rates reaching approximately 46% in severe cases.1 Prone positioning (PP) is a well-established therapeutic strategy for ARDS, offering substantial physiological and clinical benefits. Physiologically, PP improves oxygenation and reduces pleural pressure gradients, thereby decreasing lung stress and strain, two fundamental mechanisms driving ventilator-induced lung injury (VILI).2 Clinically, the protective effects of PP against VILI translate into better patient outcomes, including a 30% reduction in mortality risk among patients with moderate-to-severe ARDS.3,4
Despite the physiological and clinical benefits of PP, this strategy remains underutilized in ARDS patients worldwide.5 Barriers to implementation include the high workload associated with the technique and concerns over an increased risk of complications, such as dislodgement of vascular catheters or endotracheal tubes (ETT) during patient mobilization.6 According to current guidelines, repositioning is advised every 12–16 h per day, alternating between prone and supine positions.7,8 To address these challenges, some authors have proposed extending the duration of PP to enhance adherence and reduce adverse events.6
The optimal duration of PP is a topic of ongoing debate.2 The landmark PROSEVA trial demonstrated a significant reduction in mortality in severe ARDS using a conventional PP (CPP) protocol of at least 16 consecutive hours per day,9 with a mean session duration of 17 ± 3 h, and a total of 4 ± 4 sessions per patient. However, there is no physiological rationale for limiting PP to 16 h. Emerging evidence supports prolonged (i.e. extended) PP, defined as sessions lasting over 24 h or continuing until clinical improvement. Prolonged PP (PPP) may further optimize lung protection by minimizing disruptions from patient repositioning, which can compromise oxygenation.10,11 Additionally, PPP could offer organizational advantages, such as reduced ICU staff workload and fewer adverse events related to patient mobilization.6 Nevertheless, these benefits must be weighed against potential risks, including an increased incidence of pressure injuries with a longer time in PP.12
Available evidence comparing CPP and PPP in ARDS patients mainly comes from observational clinical studies, and some pilot randomized clinical trials (RCT) with variable or inconclusive results.6 Moreover, previous systematic reviews on this topic lack rigorous methodologies, limiting their applicability in clinical practice.13,14 This systematic review with meta-analysis addresses these gaps and aims to compare the efficacy and safety of CPP versus PPP in ARDS patients.
MethodsThe methodology of this work was predefined, and it is fully available online.15 We followed Cochrane guidelines for systematic reviews of prognostic factors16 and registered the review in PROSPERO (CRD42024572441), in alignment with the Preferred Reporting Items for Systematic review and Meta-Analysis (PRISMA) statement.17
Literature searchWe thoroughly searched Embase, Scopus, and PubMed from inception up to Feb, 2026. Our PICO research question was defined by a population of adult patients diagnosed with ARDS, an intervention of PPP, and a comparison with CPP. Efficacy outcomes investigated were short-term mortality, ICU length of stay (ICU-LOS), and mechanical ventilation (MV) duration. Safety outcomes were pressure injuries (PI), ETT dislodgement, loss of vascular access, and edema. Specific search strategies for each database are listed in the protocol15 and incorporate free text for all synonyms of Prolonged prone positioning. No additional filters were included besides the ones reported in the strings. No restrictions were placed on language, date, or publication status. Additionally, we manually scrutinized the reference lists of eligible studies and consulted with experts on the topic to uncover potentially missing relevant articles.
Study selection and definitionsWe included primary articles, encompassing both RCTs and non-randomized studies (NRS), involving adults diagnosed with ARDS according to Berlin or AECC criteria,18,19 with Pa/FiO2 ratio less than 200 mmHg at the time that PP was indicated. Thus, we included observational and controlled trials that reported outcomes comparing a PPP group to a CPP one. Due to the expected small number of RCTs, their limited sample sizes, and the infrequent reporting of rare events, we opted to include prospective and retrospective observational studies that were not appraised as “Critical” Risk of Bias (RoB).20
Conventional PP was defined as any PP protocol that indicates routine daily supination in all cycles (i.e., daily PP sessions < 24 h). PPP was defined as any prone position protocol that does not include an indication for routine daily supination (i.e. ≥24 h of continuous prone). Mortality was defined as ICU mortality, in-hospital mortality, or, at most, 30-day mortality, in that preferential order. ICU-LOS and MV duration were counted as complete days. PI frequency was considered as the number of patients with PI, in any body area, and of any severity. ETT dislodgement encompasses loss, displacement, or obstruction of endotracheal, nasogastric, or other invasive pharyngeal devices during PP. Loss of vascular access included events of dislodgement or removal of either arterial or venous, either peripheral or central vascular access. Finally, edema was considered if it was present in any body area, irrespective of the severity.15
Data extraction and risk of bias assessmentSearch results were first screened by title and abstract. After duplication deletion, two investigators independently collected all eligible articles for full-text review (see the Suppl. Material). A third reviewer solved disagreements.
Likewise, the Risk of Bias (RoB) was independently evaluated by two reviewers. Cochrane ROB-2 tool was used for RCTs,21 consisting of domains 1–5. Risk Of Bias In Nonrandomized Studies-of Interventions (ROBINS-I) was used for NRSs assessment.22
Statistical analysisFor dichotomous outcomes, Random Effect Models (REM) were used to pool Risk Ratios (RR), which were calculated from 2 × 2 tables for RCTs.23–27 In two NRSs,28,29 adjusted Risk Ratios (aRR) were calculated from post-score-weighting data. aRR values were derived from adjusted Hazard,30 or Odds Ratios31 when necessary32,33 (see Suppl. Material). For the meta-analysis of loss of vascular access, Mantel-Haenszel Odds Ratio tests (Fixed-effect models) without continuity correction were applied due to the rarity of events.34,35 For continuous outcomes, REMs were used with mean difference (MD) as the effect measure after converting measures of central tendency into mean and standard deviation.36 Once again, in one NRS, adjusted mean differences were obtained from post-score-weighting data.28
Heterogeneity was assessed by visual inspection and taking into consideration I2 statistics (where I2 > 50% and P-value < .10 is usually considered Relevant heterogeneity).16
Certainty of evidenceWe assessed the certainty of evidence for each outcome using the GRADE approach. In alignment with these recommendations, we analyzed only the available studies with the lowest risk of bias and without serious.37 Summary of Findings (SoF) tables were generated to present the outcomes relying on models that accounted for heterogeneity (corresponding to the sensitivity analyses for Mortality and PI outcomes). We adopted a partially contextualized approach,38 using thresholds based on absolute differences aligned with the relative importance of each outcome.
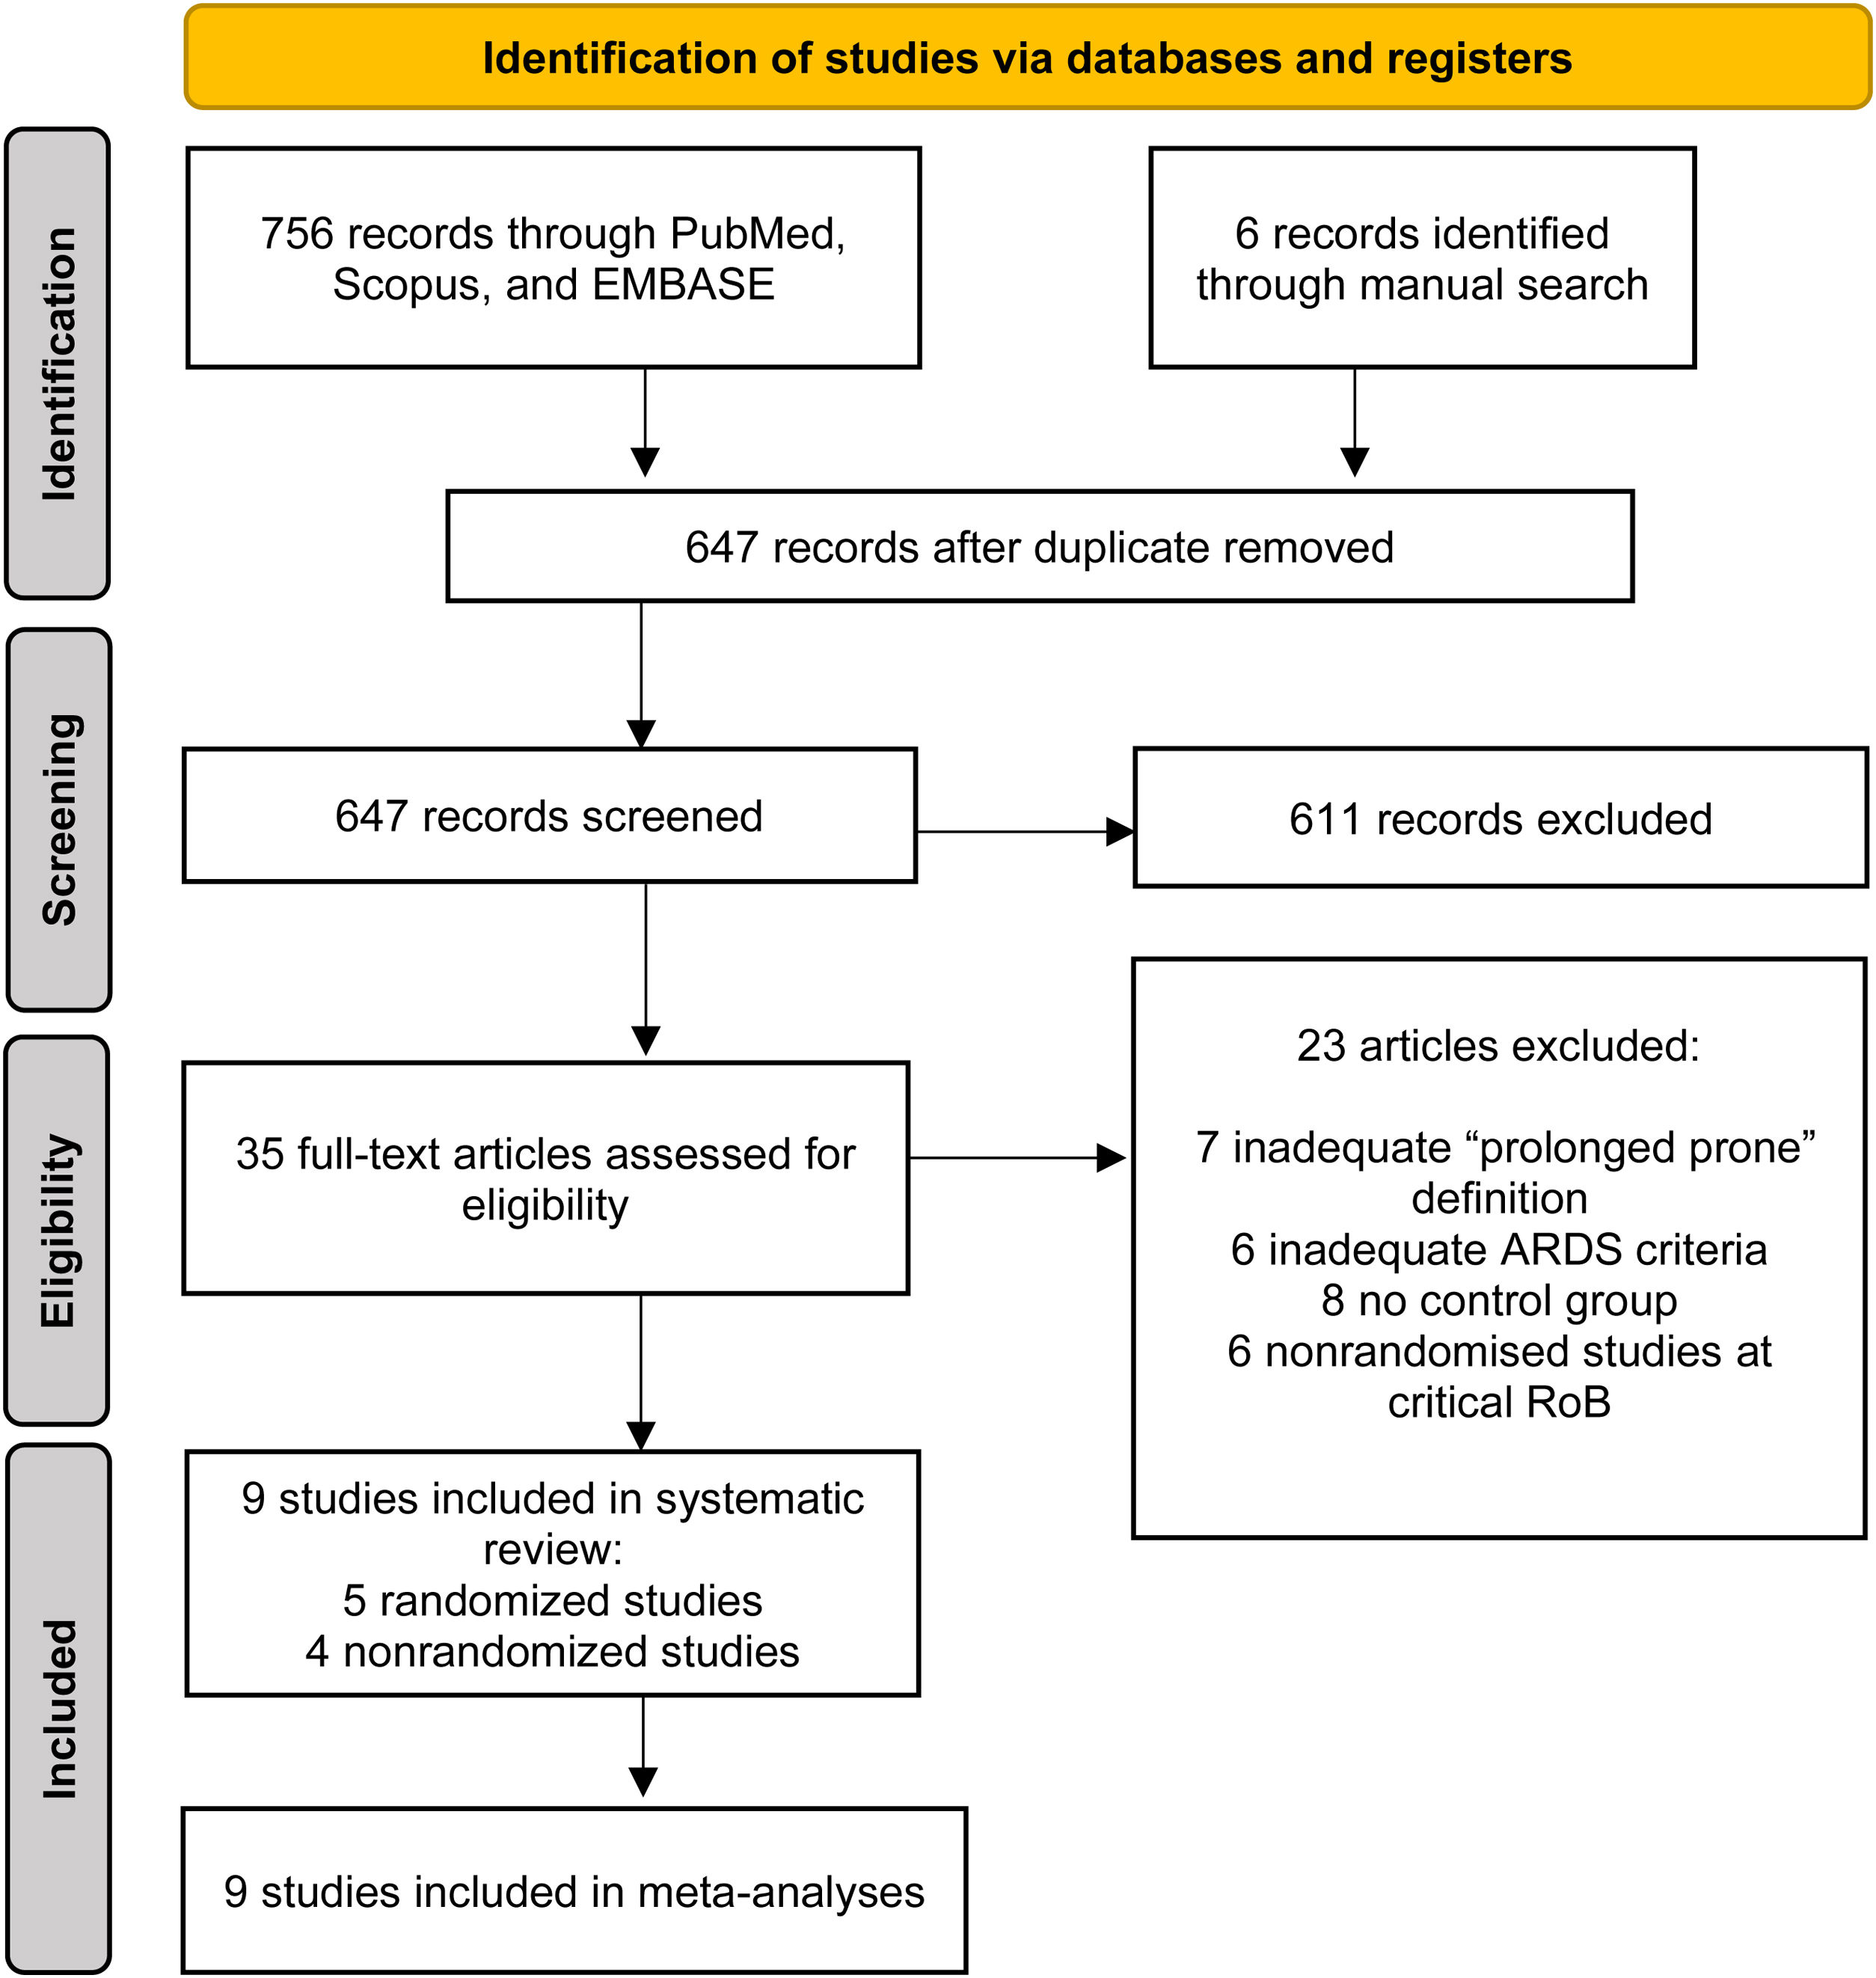
ResultsSelected studiesAfter discarding duplicates, we obtained 647 studies; 35 articles passed the primary screening, and nine studies were finally included (Fig. 1). Six NRSs studies were excluded due to Critical RoB for all outcomes (see Supplementary Material).
We included five RCTs,23–27 and four NRSs.28–31 The RCTs involved a total of 329 patients, while the NRSs included a total of 2295 patients. COVID-19 was the primary etiology of most of the 2624 patients, except for 45 patients from the study by Hsu et al.
Two RCTs26,27 assigned the treatment arm based on the duration of the first prone session, regardless of subsequent sessions duration, while all the other RCTs23–25 assigned participants to either a conventional or a prolonged strategy for each session throughout the trial. All NRSs classified patients according to the duration of the first prone session. Among the included NRSs, one adopted a Target Trial framework,27 while the others were adjusted cohort studies.28–30
For the efficacy outcomes, most studies reported short-term mortality as 28 or 30-day mortality, and one reported In-hospital mortality; with the MV duration and ICU-LOS being reported in four studies. All NRSs reported adjusted estimates, three utilized inverse probability treatment weighting analysis (IPTW),27–29 and one multivariate regression.30 Additionally, some studies27,28 reported various other adjustment methods. Regarding safety outcomes, six studies reported PIs (four in any body site,23,25–27 and one on the ventral surface24). Three studies described ETT dislodgement rates, although one documented no events. None of the NRSs reported safety outcome data.
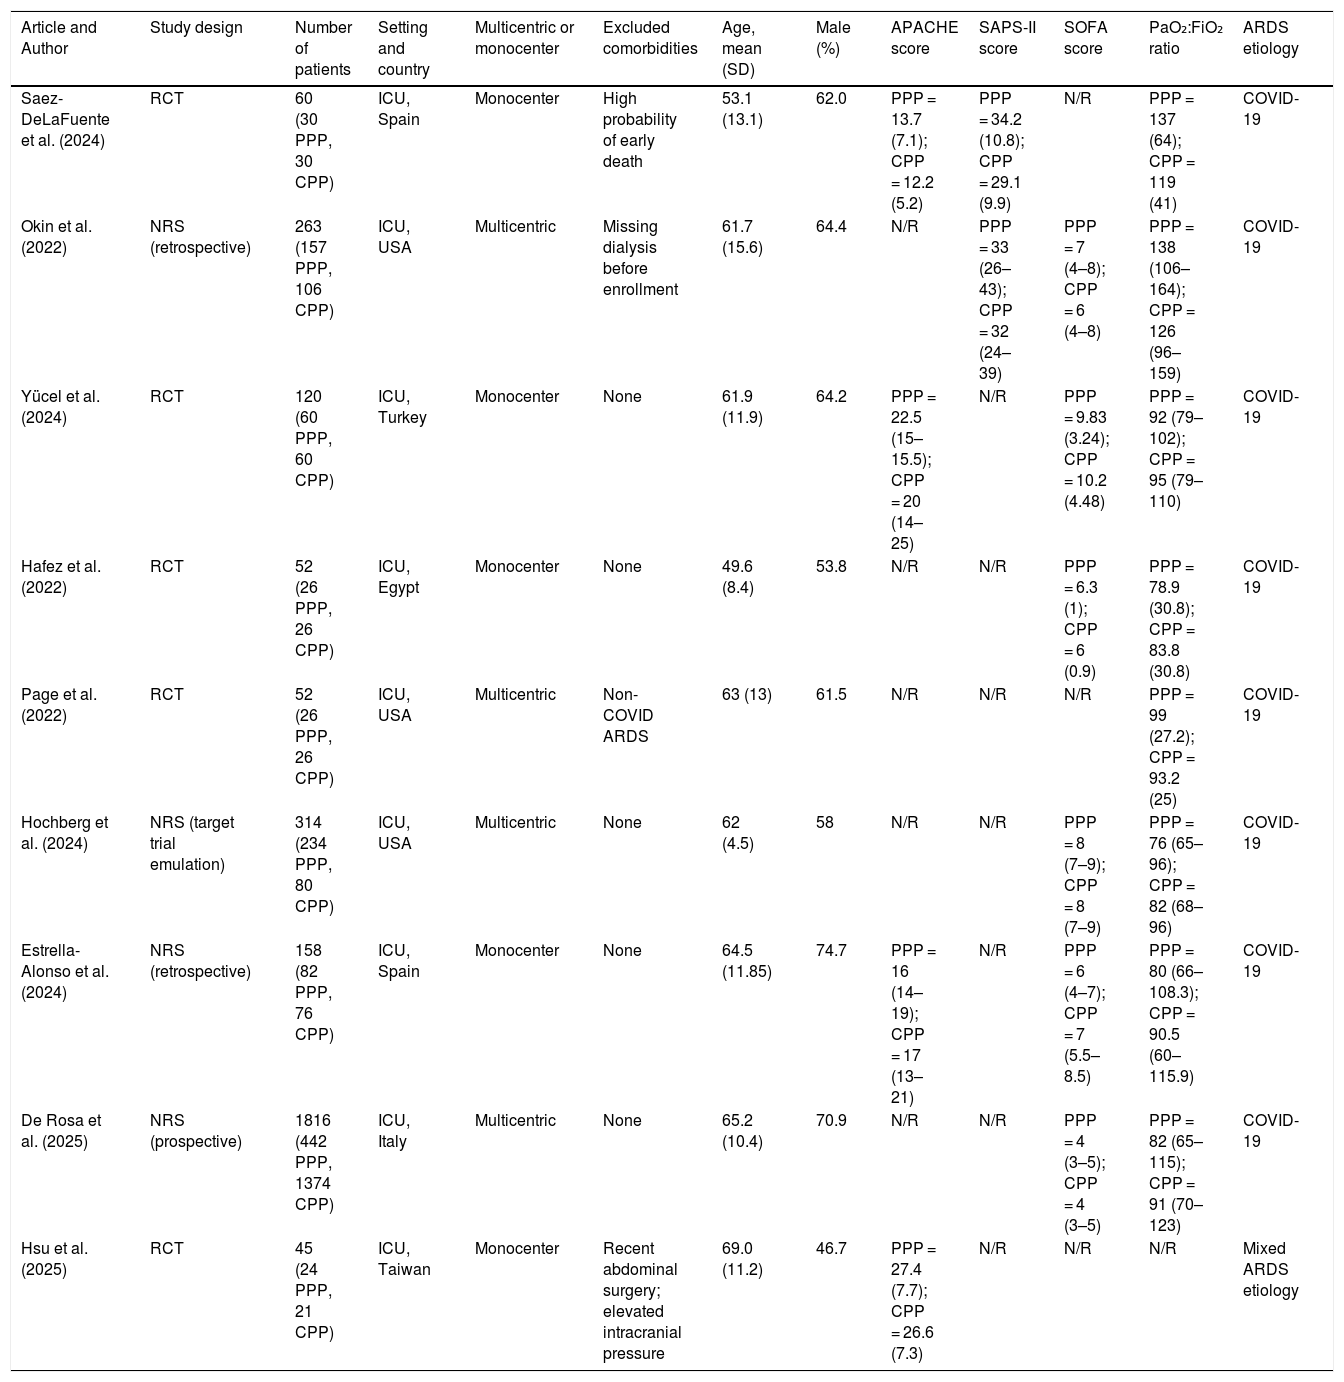
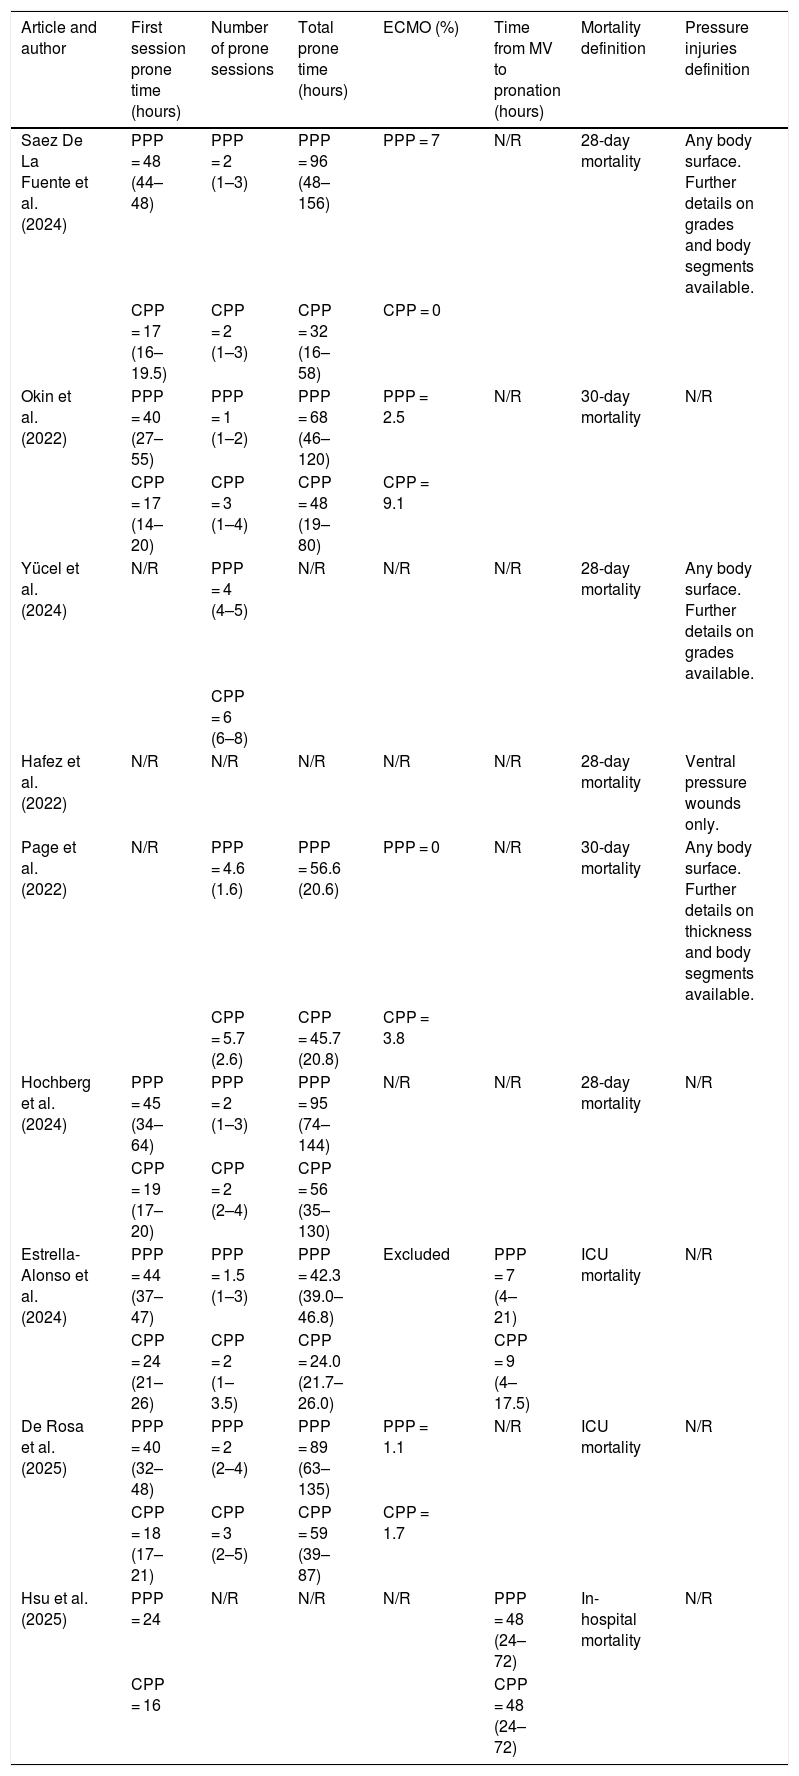
Table 1 describes the characteristics of the included patients. More details about prone positioning and outcomes assessed are shown in Table 2.
Characteristics of patients in included studies.
| Article and Author | Study design | Number of patients | Setting and country | Multicentric or monocenter | Excluded comorbidities | Age, mean (SD) | Male (%) | APACHE score | SAPS-II score | SOFA score | PaO₂:FiO₂ ratio | ARDS etiology |
|---|---|---|---|---|---|---|---|---|---|---|---|---|
| Saez-DeLaFuente et al. (2024) | RCT | 60 (30 PPP, 30 CPP) | ICU, Spain | Monocenter | High probability of early death | 53.1 (13.1) | 62.0 | PPP = 13.7 (7.1); CPP = 12.2 (5.2) | PPP = 34.2 (10.8); CPP = 29.1 (9.9) | N/R | PPP = 137 (64); CPP = 119 (41) | COVID-19 |
| Okin et al. (2022) | NRS (retrospective) | 263 (157 PPP, 106 CPP) | ICU, USA | Multicentric | Missing dialysis before enrollment | 61.7 (15.6) | 64.4 | N/R | PPP = 33 (26–43); CPP = 32 (24–39) | PPP = 7 (4–8); CPP = 6 (4–8) | PPP = 138 (106–164); CPP = 126 (96–159) | COVID-19 |
| Yücel et al. (2024) | RCT | 120 (60 PPP, 60 CPP) | ICU, Turkey | Monocenter | None | 61.9 (11.9) | 64.2 | PPP = 22.5 (15–15.5); CPP = 20 (14–25) | N/R | PPP = 9.83 (3.24); CPP = 10.2 (4.48) | PPP = 92 (79–102); CPP = 95 (79–110) | COVID-19 |
| Hafez et al. (2022) | RCT | 52 (26 PPP, 26 CPP) | ICU, Egypt | Monocenter | None | 49.6 (8.4) | 53.8 | N/R | N/R | PPP = 6.3 (1); CPP = 6 (0.9) | PPP = 78.9 (30.8); CPP = 83.8 (30.8) | COVID-19 |
| Page et al. (2022) | RCT | 52 (26 PPP, 26 CPP) | ICU, USA | Multicentric | Non-COVID ARDS | 63 (13) | 61.5 | N/R | N/R | N/R | PPP = 99 (27.2); CPP = 93.2 (25) | COVID-19 |
| Hochberg et al. (2024) | NRS (target trial emulation) | 314 (234 PPP, 80 CPP) | ICU, USA | Multicentric | None | 62 (4.5) | 58 | N/R | N/R | PPP = 8 (7–9); CPP = 8 (7–9) | PPP = 76 (65–96); CPP = 82 (68–96) | COVID-19 |
| Estrella-Alonso et al. (2024) | NRS (retrospective) | 158 (82 PPP, 76 CPP) | ICU, Spain | Monocenter | None | 64.5 (11.85) | 74.7 | PPP = 16 (14–19); CPP = 17 (13–21) | N/R | PPP = 6 (4–7); CPP = 7 (5.5–8.5) | PPP = 80 (66–108.3); CPP = 90.5 (60–115.9) | COVID-19 |
| De Rosa et al. (2025) | NRS (prospective) | 1816 (442 PPP, 1374 CPP) | ICU, Italy | Multicentric | None | 65.2 (10.4) | 70.9 | N/R | N/R | PPP = 4 (3–5); CPP = 4 (3–5) | PPP = 82 (65–115); CPP = 91 (70–123) | COVID-19 |
| Hsu et al. (2025) | RCT | 45 (24 PPP, 21 CPP) | ICU, Taiwan | Monocenter | Recent abdominal surgery; elevated intracranial pressure | 69.0 (11.2) | 46.7 | PPP = 27.4 (7.7); CPP = 26.6 (7.3) | N/R | N/R | N/R | Mixed ARDS etiology |
For severity scores (APACHE, SAPS-II and SOFA) data is reported as mean (SD) or median (Q1–Q2).
RCT: Randomized controlled trial; NRS: non-randomized study (observational study); PPP: prolonged prone position; CPP: Conventional prone position; N/R: not reported.
Prone positioning and outcomes assessed in the included studies.
| Article and author | First session prone time (hours) | Number of prone sessions | Total prone time (hours) | ECMO (%) | Time from MV to pronation (hours) | Mortality definition | Pressure injuries definition |
|---|---|---|---|---|---|---|---|
| Saez De La Fuente et al. (2024) | PPP = 48 (44–48) | PPP = 2 (1–3) | PPP = 96 (48–156) | PPP = 7 | N/R | 28-day mortality | Any body surface. Further details on grades and body segments available. |
| CPP = 17 (16–19.5) | CPP = 2 (1–3) | CPP = 32 (16–58) | CPP = 0 | ||||
| Okin et al. (2022) | PPP = 40 (27–55) | PPP = 1 (1–2) | PPP = 68 (46–120) | PPP = 2.5 | N/R | 30-day mortality | N/R |
| CPP = 17 (14–20) | CPP = 3 (1–4) | CPP = 48 (19–80) | CPP = 9.1 | ||||
| Yücel et al. (2024) | N/R | PPP = 4 (4–5) | N/R | N/R | N/R | 28-day mortality | Any body surface. Further details on grades available. |
| CPP = 6 (6–8) | |||||||
| Hafez et al. (2022) | N/R | N/R | N/R | N/R | N/R | 28-day mortality | Ventral pressure wounds only. |
| Page et al. (2022) | N/R | PPP = 4.6 (1.6) | PPP = 56.6 (20.6) | PPP = 0 | N/R | 30-day mortality | Any body surface. Further details on thickness and body segments available. |
| CPP = 5.7 (2.6) | CPP = 45.7 (20.8) | CPP = 3.8 | |||||
| Hochberg et al. (2024) | PPP = 45 (34–64) | PPP = 2 (1–3) | PPP = 95 (74–144) | N/R | N/R | 28-day mortality | N/R |
| CPP = 19 (17–20) | CPP = 2 (2–4) | CPP = 56 (35–130) | |||||
| Estrella-Alonso et al. (2024) | PPP = 44 (37–47) | PPP = 1.5 (1–3) | PPP = 42.3 (39.0–46.8) | Excluded | PPP = 7 (4–21) | ICU mortality | N/R |
| CPP = 24 (21–26) | CPP = 2 (1–3.5) | CPP = 24.0 (21.7–26.0) | CPP = 9 (4–17.5) | ||||
| De Rosa et al. (2025) | PPP = 40 (32–48) | PPP = 2 (2–4) | PPP = 89 (63–135) | PPP = 1.1 | N/R | ICU mortality | N/R |
| CPP = 18 (17–21) | CPP = 3 (2–5) | CPP = 59 (39–87) | CPP = 1.7 | ||||
| Hsu et al. (2025) | PPP = 24 | N/R | N/R | N/R | PPP = 48 (24–72) | In-hospital mortality | N/R |
| CPP = 16 | CPP = 48 (24–72) |
For prone data (times and number of sessions) data is reported as mean (SD) or median (Q1–Q2).
RCT: Randomized controlled trial; NRS: non-randomized study (observational study); PPP: prolonged prone position; CPP: Conventional prone position; N/R: not reported; ECMO: Extracorporeal membrane oxygenation.
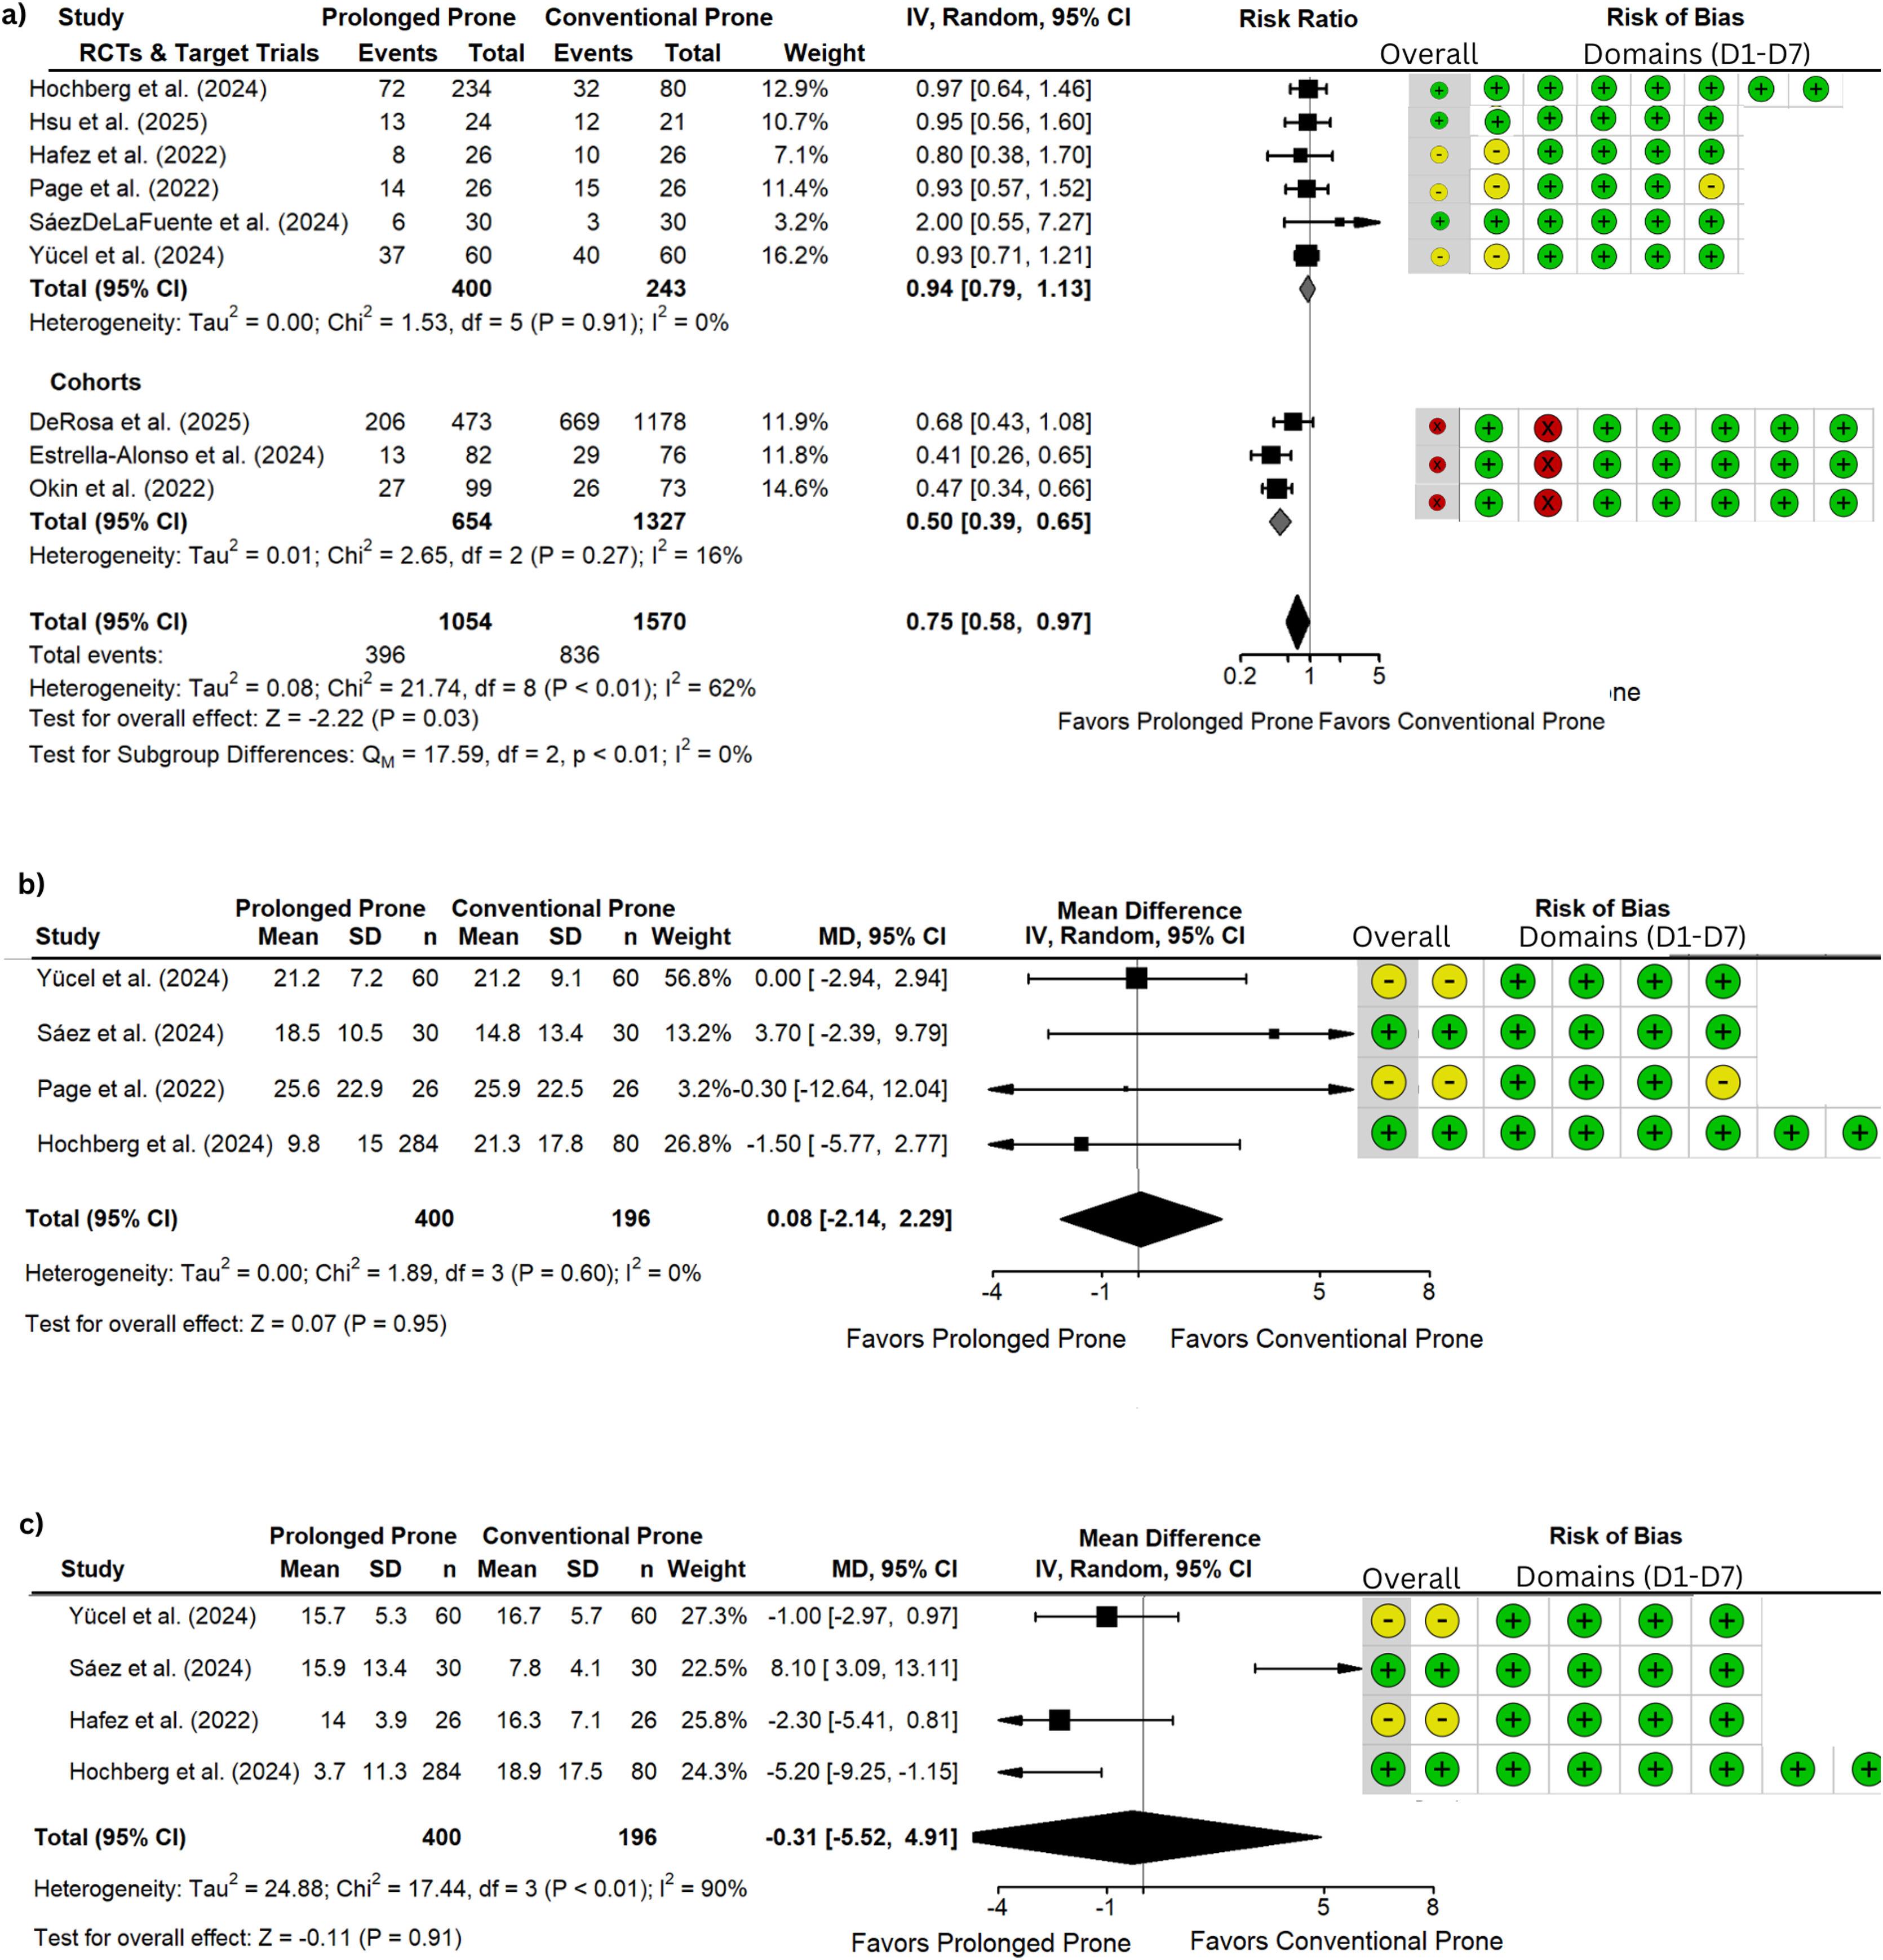
When all five randomized RCTs and NRSs were included, PPP was associated with lower short-term mortality compared with CPP (RR 0.75, 95% CI 0.58–0.97; Fig. 2a). The sensitivity analysis including RCTs and a Target Trial Emulation showed no significant difference between PPP and CPP (RR 0.94, 95% CI 0.79–1.13).
Forest plot of efficacy outcomes by prolonged vs. conventional prone positioning protocol.
Efficacy outcomes are shown as follows: a) short-term mortality; b) ICU-Length of Stay (days); c) Duration of mechanical ventilation (days). For non-randomized studies (NRS), counts presented in tables are crude, but weighted estimates are adjusted. Sensitivity analyses are shown, grouping RCTs together with Target Trial Emulations vs. other NRS designs (i.e. Cohorts).
The ICU-LOS and MV duration analyses encompassed data from three RCTs,23–26 and one Target Trial.28 No relevant difference was found in these models (Fig. 2b, 2c).
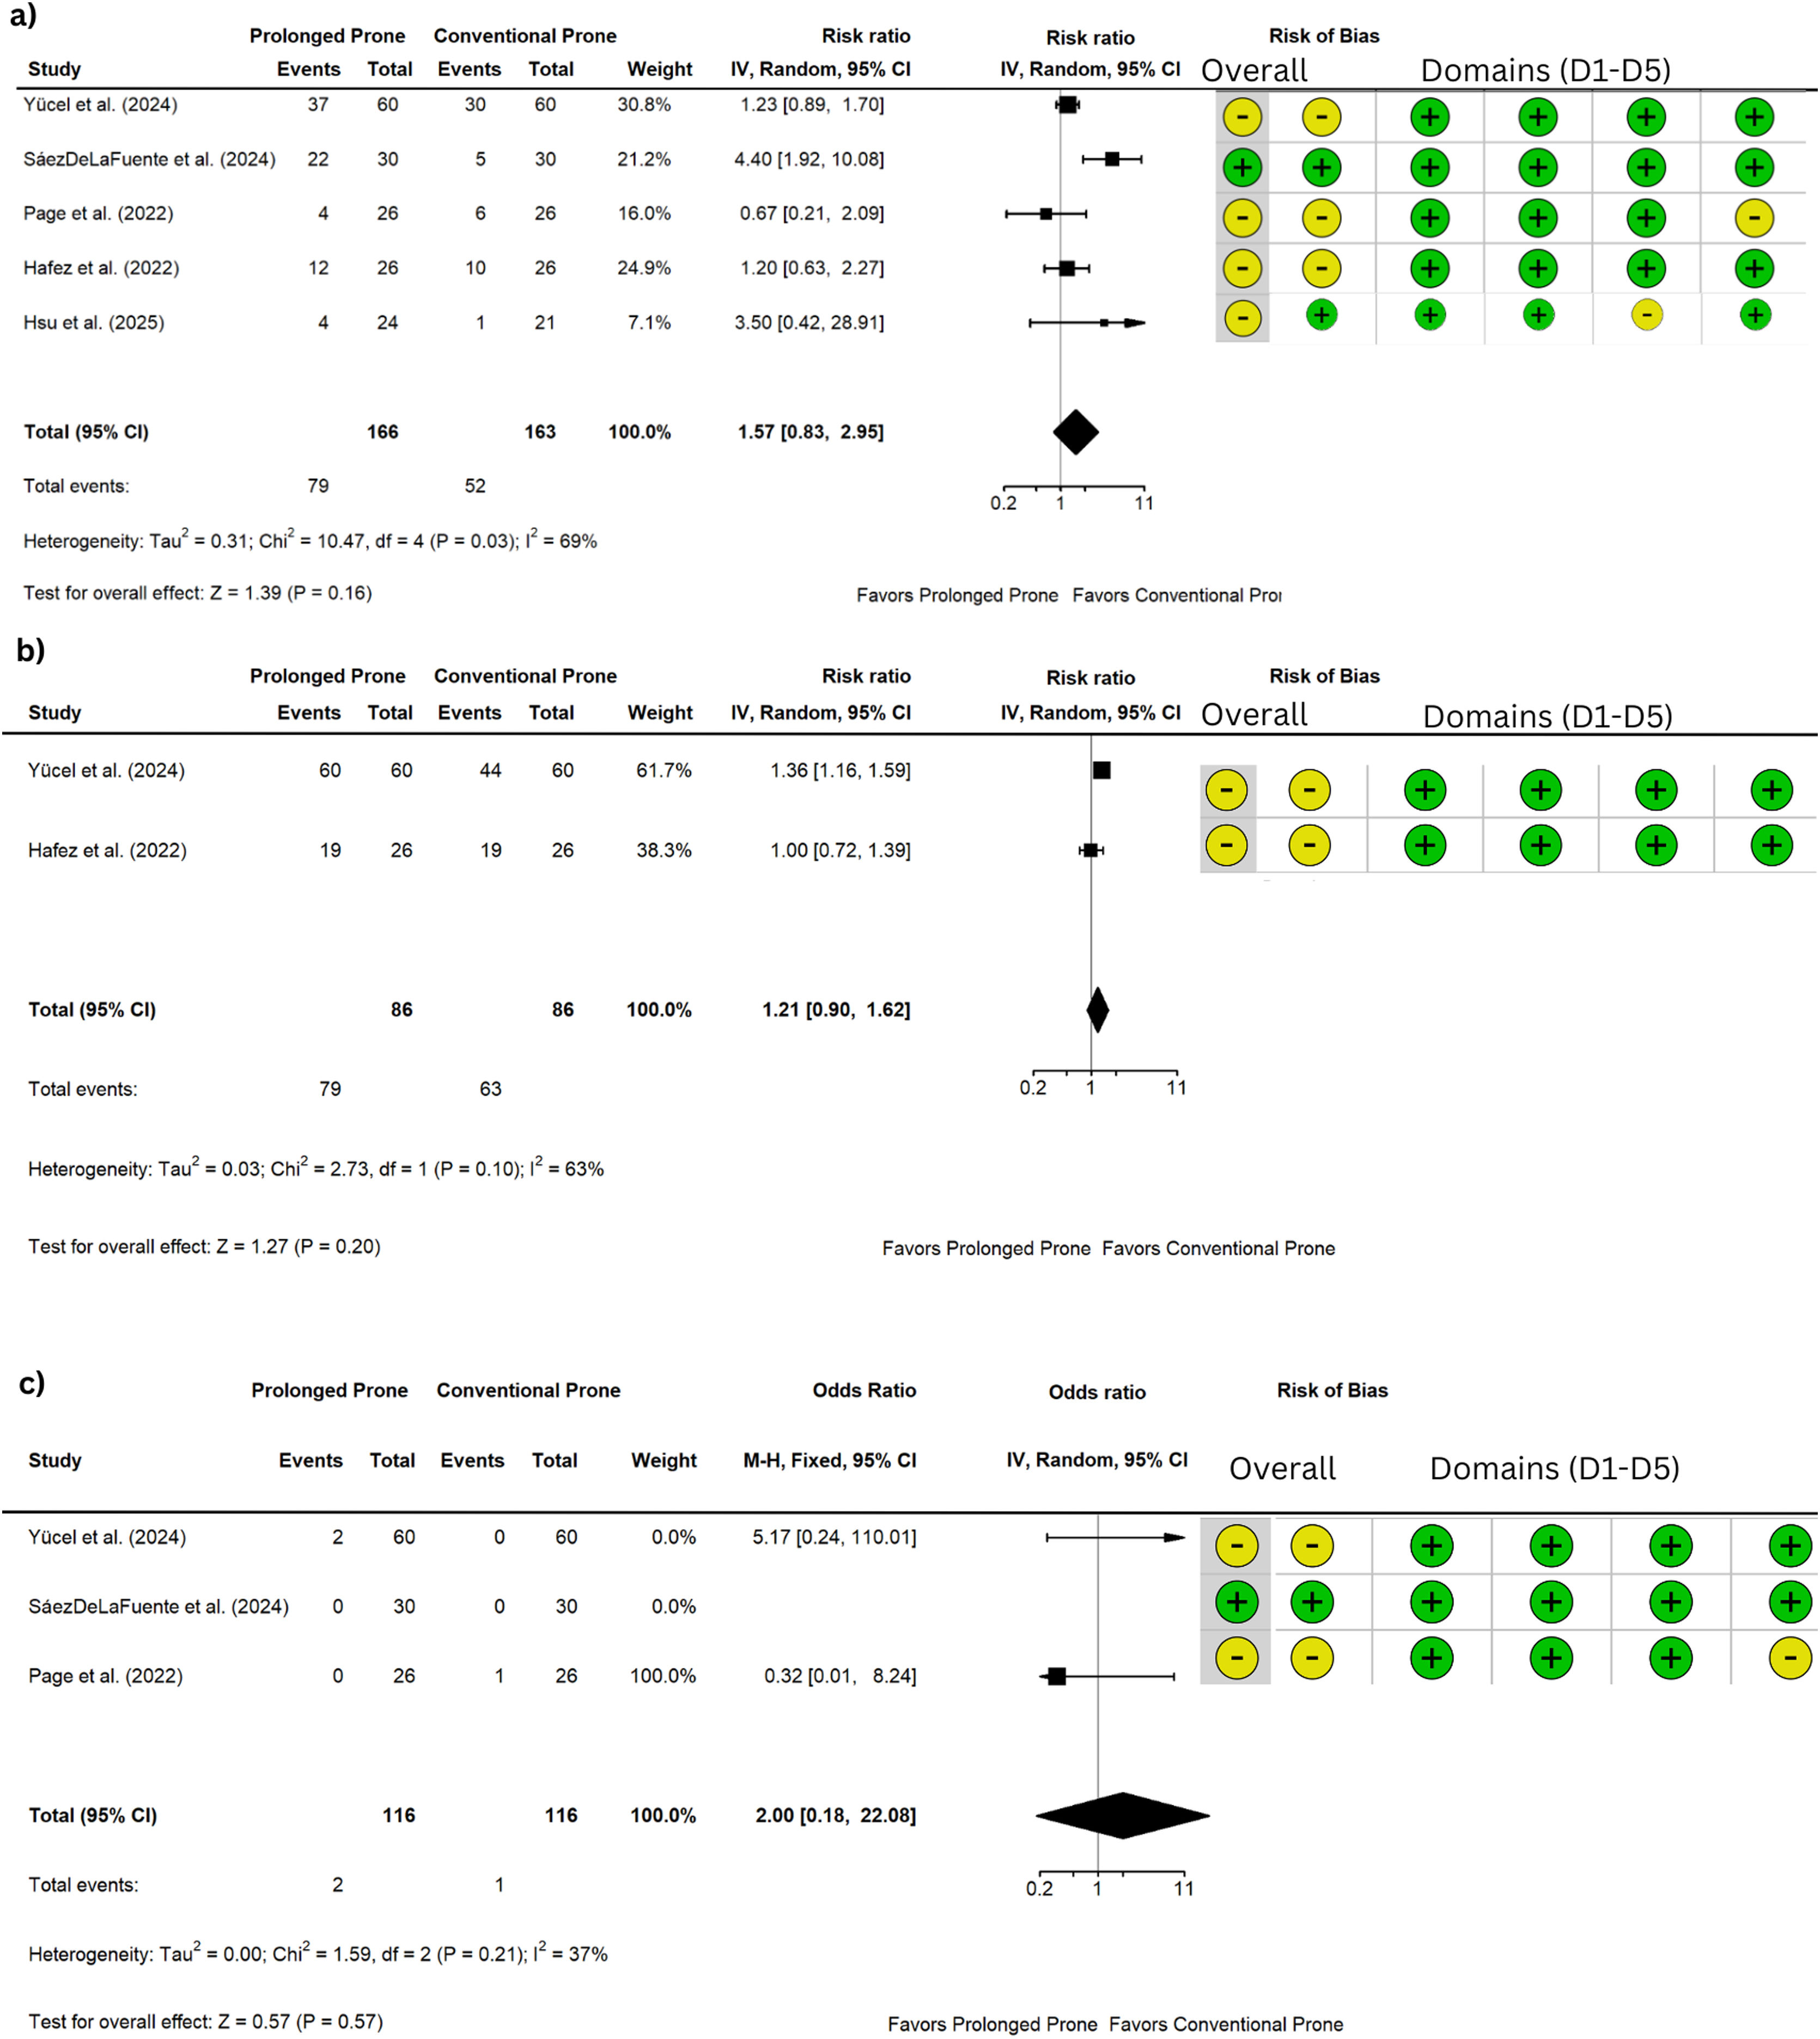
Regarding safety outcomes (Fig.3), PI was the most common adverse event, with a pooled rate of 44.3% in patients who received any PP protocol. Loss of vascular access was the less frequent adverse event related to PP, with rates near 0%. The comparison of PI, edema, and loss of vascular access between PPP and CPP included only RCTs.23,25–27 All these safety outcomes were similar between groups: RR 1.57 (95% CI 0.83–2.95) for PI, RR 1.21 (95% CI 0.90–1.62) for edema, and RR 2.0 (0.18–22.08) for loss of vascular. The reported RRs for ETT dislodgement were 0.19 and 0.32, respectively, in the two randomized controlled trials, although neither reached statistical significance. A pooled estimate could not be reliably calculated because of the low number of events. A sensitivity analysis focused on severe PIs in any body site (grade III or IV), showed similar results (RR 1.33, CI 95% 0.66–2.68; see Supplementary Material).
Heterogeneity investigationsThe primary analysis of the mortality outcome showed substantial heterogeneity (I2 = 62%), which abated when examining subgroups by study designs (i.e., RCTs/target trial and cohorts). The ICU-LOS model did not show heterogeneity (I2 = 0%). The analysis of MV duration exhibited substantial heterogeneity (I2 = 90%), mainly driven by an adverse estimate reported in one clinical trial.23 When excluding this study, the pooled mean difference for MV duration changed substantially from −0.31 days (95% CI −5.52 to 4.91) to −2.25 days (95% CI −4.45 to −0.11), and the heterogeneity resolved (I2 = 0%; see Supplementary Material).
Regarding safety outcomes, the PI and edema models were heterogeneous (I2 = 69%, and 63%, respectively) due to variations in event definitions and reporting across studies. This is evidenced by the significantly lower heterogeneity observed in the sensitivity analysis of PIs restricted to severe events on any surface. The rest of the models were relatively homogeneous.
We did not conduct further subgroup analyses investigating heterogeneity in any model due to the limited number of research articles.
Risk of biasAmong the efficacy outcomes, the overall RoB was deemed “Low” in two RCT23,27 and “some concerns” in the others,24–26 primarily due to the lack of information on allocation concealment, affecting domain 1. Additionally, one study25 was flagged with “Some concerns” in domain 5 because a prespecified protocol was unavailable in the publication. For the NRSs, the Target Trial received a classification of “Low” RoB,28 while the remaining NRSs were downgraded due to inadequate control for immortal time bias during the first 24 h of proning, yielding an overall grade of “Serious” RoB.
In assessing safety outcomes, the overall RoB was again deemed “Low” in one RCT,23 with “Some concerns” in the remaining trials.24–26
Publication biasWe did not run Egger tests or create Funnel plots because none of the models included 10 or more studies. Nevertheless, considering the extensive search that included abstracts and conference papers, we have no reason to believe any estimates were systematically omitted.
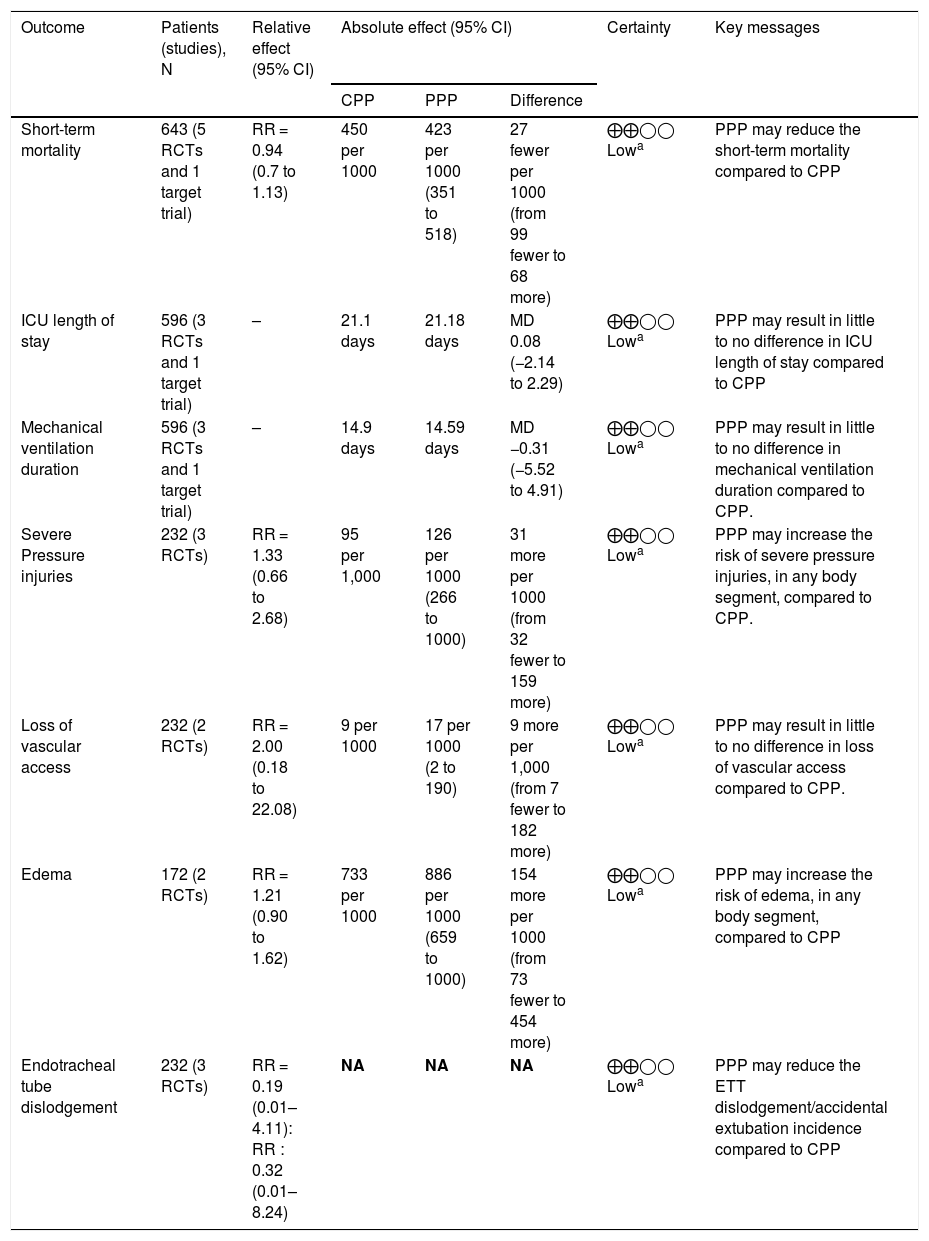
DiscussionThis systematic review with meta-analysis represents the most comprehensive synthesis to date about PPP in ARDS. In this study, with a total of 2624 patients from nine studies of ARDS mostly due to COVID-19, we found that PPP could confer some benefit in efficacy outcomes, without increasing the risk of serious safety events compared to CPP. However, the certainty of the evidence was consistently rated as low across all outcomes (see Table 3).
Certainty of evidence and summary of findings for prolonged vs conventional prone positioning in ARDS patients.
| Outcome | Patients (studies), N | Relative effect (95% CI) | Absolute effect (95% CI) | Certainty | Key messages | ||
|---|---|---|---|---|---|---|---|
| CPP | PPP | Difference | |||||
| Short-term mortality | 643 (5 RCTs and 1 target trial) | RR = 0.94 (0.7 to 1.13) | 450 per 1000 | 423 per 1000 (351 to 518) | 27 fewer per 1000 (from 99 fewer to 68 more) | ⨁⨁◯◯ Lowa | PPP may reduce the short-term mortality compared to CPP |
| ICU length of stay | 596 (3 RCTs and 1 target trial) | – | 21.1 days | 21.18 days | MD 0.08 (−2.14 to 2.29) | ⨁⨁◯◯ Lowa | PPP may result in little to no difference in ICU length of stay compared to CPP |
| Mechanical ventilation duration | 596 (3 RCTs and 1 target trial) | – | 14.9 days | 14.59 days | MD −0.31 (−5.52 to 4.91) | ⨁⨁◯◯ Lowa | PPP may result in little to no difference in mechanical ventilation duration compared to CPP. |
| Severe Pressure injuries | 232 (3 RCTs) | RR = 1.33 (0.66 to 2.68) | 95 per 1,000 | 126 per 1000 (266 to 1000) | 31 more per 1000 (from 32 fewer to 159 more) | ⨁⨁◯◯ Lowa | PPP may increase the risk of severe pressure injuries, in any body segment, compared to CPP. |
| Loss of vascular access | 232 (2 RCTs) | RR = 2.00 (0.18 to 22.08) | 9 per 1000 | 17 per 1000 (2 to 190) | 9 more per 1,000 (from 7 fewer to 182 more) | ⨁⨁◯◯ Lowa | PPP may result in little to no difference in loss of vascular access compared to CPP. |
| Edema | 172 (2 RCTs) | RR = 1.21 (0.90 to 1.62) | 733 per 1000 | 886 per 1000 (659 to 1000) | 154 more per 1000 (from 73 fewer to 454 more) | ⨁⨁◯◯ Lowa | PPP may increase the risk of edema, in any body segment, compared to CPP |
| Endotracheal tube dislodgement | 232 (3 RCTs) | RR = 0.19 (0.01–4.11): RR : 0.32 (0.01–8.24) | NA | NA | NA | ⨁⨁◯◯ Lowa | PPP may reduce the ETT dislodgement/accidental extubation incidence compared to CPP |
CI: confidence interval; MD: mean difference; RR: risk ratio; PPP: prolonged prone positioning; CPP: conventional prone positioning a. It was downgraded two levels because of serious risk of bias and imprecision. b. It was downgraded three levels because of serious risk of bias, inconsistency, and imprecision.
When considering all the available evidence in a pooled estimate –i.e. RCTs and all NRSs– PPP showed a benefit in reducing short-term mortality; nevertheless, this was driven mainly by low-quality observational studies in which patients who died within the first 24 h were automatically assigned to the CPP group. In the sensitivity analysis that included RCTs and one high-quality observational study (target trial emulation design) no significant difference was observed between PPP and CPP. Given the study's rigorous methodology (namely, adequate control for confounding, and mitigation of immortal time bias) the inclusion of these study designs together is well justified. This is consistent with evidence showing strong agreement between RCTs and target trial emulations when robust methods are applied.38,39 Therefore, the estimate derived from RCTs and the emulation study was prioritized in the Summary of Findings table, as it likely provides a less biased estimate of the intervention effect.
Notably, the five available RCTs comparing prolonged and conventional PP included small sample sizes (26–60 patients per arm), limiting their statistical power to detect small-to-moderate treatment effects. Most trials showed a trend toward lower mortality with PPP compared with CPP, except for the study by Saez et al.23 Importantly, this trial enrolled patients with comparatively higher baseline PaO₂/FiO₂ ratios than those reported in other studies, suggesting lower initial ARDS severity.23
The other two efficacy outcomes —ICU LOS and MV duration— were assessed across three RCTs and one target trial, with findings showing no major differences between conventional and prolonged PP strategies. Once again, Saez et al. diverged from the rest of the studies, consistently favoring CPP. Of note, these authors employed a substantially more aggressive neuromuscular blockade agents (NMBA) protocol.23 The use of ECMO and other supportive therapies was inconsistently reported across studies. These differences in co-interventions and baseline disease severity may have modified or attenuated the potential benefits of prolonged prone positioning.
In the current meta-analysis, safety outcomes analysis only included data from RCTs. We found no significant differences between CPP and PPP groups regarding PI, edema, and loss of vascular access. Similarly, individual estimates for ETT dislodgement did not differ significantly between groups; however, a pooled risk ratio could not be calculated because of mathematical nonconvergence resulting from the very low number of events. Although PIs tended to be more frequent in the PPP arm, rates declined importantly, and the risk ratio was even less pronounced when the analysis was restricted to severe or high-grade PI, affecting any body surface. Consequently, we conclude that PPP may carry a slightly higher risk of severe PI, edema, and ETT dislodgement.
While historically, trials and guidelines have recommended 12–16 h per day of CPP,7–9 no physiological rationale limits the duration of prone sessions.2 Physiological rationale for extended PP includes sustained improvements in ventilation parameters, such as PaFi ratios and static compliance, which often continue to evolve beyond the first 24 h of proning.28,30,31,40 Organizationally, prolonged sessions may simplify ICU logistics and reduce workload associated with daily repositioning, potentially improving adherence to prone protocols.6 In this sense, our findings align with a prior meta-analysis that reported a non-significant odds ratio of 0.79 (95% CI: 0.57–1.11) for mortality, slightly favoring PPP protocols over CPP.14 However, it is important to note that the sample included in that analysis were largely based on unadjusted estimates, among other major methodological limitations discussed elsewhere.13 Adverse event rates were generally low in our dataset. Overall, our findings suggest that PPP is a safe intervention, with minor, manageable risks that can be effectively mitigated through appropriate staff training and standardized nursing protocols.6
This study is limited by the small number and size of high-quality RCTs, which were underpowered. Most included patients had COVID-19-related ARDS, limiting generalizability to other etiologies. Although NRSs studies were selected to minimize bias, residual confounding remains likely. Differences in co-interventions, such as sedation and neuromuscular blockade, may also have influenced results. The ongoing RCT “e-Prone” (NCT06854627) comparing PPP with CPP in patients with moderate-to-severe ARDS may provide further evidence on this issue.
ConclusionPP may reduce short-term mortality in COVID-19-related ARDS without increasing serious adverse events, but evidence certainty remains low. Further robust trials in broader ARDS populations are needed. Until then, PPP is a reasonable alternative to CPP in selected ICU settings, particularly where reducing repositioning frequency is advantageous.
Authors’ contributionsConceptualization: Abraham I. J. Gajardo, Santiago Ferrière-Steinert, José Ramos Rojas, Alejandro Bruhn, Rodrigo A Cornejo.
Formal analysis: Santiago Ferrière-Steinert, Maximiliano de la Barra, Alexandra Neman, Tamara Vergara Cerón, Jose Ramos-Rojas, Roberto Brito.
Project administration: Abraham I. J. Gajardo, Santiago Ferrière-Steinert, Rodrigo A Cornejo.
Resources: Abraham I. J. Gajardo, Rodrigo A Cornejo.
Supervision: Abraham I. J. Gajardo, Rodrigo A Cornejo.
Validation: Abraham I. J. Gajardo, Santiago Ferrière-Steinert, Alejandro Bruhn, Rodrigo A Cornejo.
Writing – original draft: Abraham IJ. Gajardo, Santiago Ferrière-Steinert, Maximiliano de la Barra, Alexandra Neman, Tamara Vergara Cerón, Jose Ramos-Rojas, Roberto Brito.
Writing – review & editing: Abraham I. J. Gajardo, José Ramos Rojas, Roberto Brito, Alejandro Bruhn, Rodrigo A Cornejo.
Declaration of Generative AI and AI-assisted technologies in the writing processArtificial intelligence tools were used exclusively for language editing. The authors are fully responsible for the content of the manuscript.
FundingThis research did not receive any specific grant from funding agencies in the public, commercial, or not-for-profit sectors.
The authors declare no competing financial interests or personal relationships that could have influenced the work reported in this paper.
The authors thank the Intensive Care Unit team at Hospital Clínico Universidad de Chile for their support during the development of this work.
The following is Supplementary data to this article:




