



In the past 25 years, oncologic critical care has grown exponentially from anonymity to becoming a significant force in the field. Small groups of intensivists around the world have contributed to the increasing awareness, changing intensive care unit admission guidelines to reprioritize cancer patients, and to the proliferation of education and development of research oncologic networks. Critically ill cancer patients have all benefited from the recent publication of the foundational bases for the subspecialty, the rapid dissemination of knowledge through webinars and congresses, and the formation of an international professional society. These advances have been made possible through transcontinental collaboration between international networks such as the Oncologic Critical Care Research Network (ONCCC-R-NET), professional societies like the Spanish Society of Intensive and Critical Care Medicine and Coronary Units (SEMICYUC), and federations including the Pan-American and Iberian Federation of Critical and Intensive Care (FEPIMCTI) and the World Federation of Intensive and Critical Care (WFICC). Global educational activities have gained momentum with strong initiatives and collaboration between them, changing the way we perceive and care for oncologic critically ill patients. Despite all these successful endeavors, there is much to do. In this article, we describe the clinical context surrounding these activities, the associated globalization efforts, the strategic rationale driving them, and opportunities we see emerging. In this issue of the journal, we also bring you a collection of outstanding collaborative works that will further enrich our knowledge, generate research ideas, and benefit critically ill cancer patients so in need of our care.
En los últimos 25 años, los cuidados críticos oncológicos han crecido de forma exponencial, pasando del anonimato a convertirse en una fuerza significativa dentro del campo. Pequeños grupos de intensivistas de todo el mundo han contribuido a aumentar la concienciación, a modificar las guías de ingreso en las unidades de cuidados intensivos para repriorizar a los pacientes oncológicos y a promover la educación y el desarrollo de redes de investigación en oncología crítica. Los pacientes oncológicos críticos se han beneficiado de la reciente publicación de los fundamentos de la subespecialidad, de la rápida difusión del conocimiento a través de seminarios web y congresos, y de la creación de una sociedad profesional internacional. Estos avances han sido posibles gracias a la colaboración transcontinental entre redes internacionales como la ONCCC-R-NET, sociedades profesionales como la SEMICYUC, y federaciones como la FEPIMCTI y la WFICC. Las actividades educativas globales han ganado un notable impulso gracias a sólidas iniciativas y a la colaboración entre estas organizaciones, transformando nuestra percepción y la atención que proporcionamos a los pacientes oncológicos críticamente enfermos. A pesar de todos estos logros, aún queda mucho por hacer. En este artículo describimos el contexto clínico que rodea estas actividades, los esfuerzos de globalización asociados, la lógica estratégica que los impulsa y las oportunidades emergentes que identificamos. En esta monografía, además, presentamos una colección de trabajos colaborativos excepcionales que enriquecerán aún más nuestro conocimiento, generarán nuevas líneas de investigación y beneficiarán a los pacientes oncológicos críticamente enfermos, tan necesitados de nuestros cuidados.
Over recent decades, the care of critically ill patients with cancer has undergone a profound transformation. What was historically considered a clinical profile with limited therapeutic options and low eligibility for admission to intensive care units (ICUs) has become—thanks to advances in diagnostics, treatment, and life support—a group fully integrated into the routine practice of Intensive Care Medicine.1–3 This paradigm shift reflects not only the evolution of oncologic strategies—shaped by immunotherapy, targeted therapies, CAR-T cells, and precision medicine—but also the development of a more proactive, humanistic, and evidence-based vision within modern ICUs.4
The magnitude of this phenomenon is undeniable.5 The rising incidence of cancer and improved overall survival have steadily increased the need for specialized intensive care in accordance with current epidemiological trends.6 These advances have not only contributed to a significant improvement in both hospital and long-term survival among these patients but have also highlighted the importance of addressing the physical, cognitive, and emotional sequelae that may emerge after prolonged ICU stays, particularly in individuals with additional vulnerability.7 The prevention and management of post–intensive care syndrome (PICS), together with effective humanization strategies, have thus become essential components of a truly comprehensive approach.8
Within this scenario, Intensive Care Medicine plays a central role. The intensivist is positioned at the core of complex decision-making, physiological stabilization, and multidisciplinary coordination with oncology, hematology, pharmacy, emergency medicine, and other medical specialties.9 Yet this role extends beyond acute management: it also requires a long-term perspective that incorporates quality of life, functional recovery, and the reduction of sequelae among survivors.7 At this point, humanization takes on increasing importance. Patient-centered care, open and honest communication, family engagement, shared decision-making, and early rehabilitation strategies must all be inseparable elements of the care model in oncologic critical care.10,11
The global expansion of oncologic critical care, driven by international scientific societies and research networks, is generating more robust and comparable evidence across countries. In this advancement, collaboration among the Spanish Society of Intensive and Critical Care Medicine and Coronary Units (SEMICYUC),12 together with international critical care networks and scientific organizations such as the World Federation of Intensive and Critical Care (WFICC),13 has become essential to strengthening global progress in oncologic critical care. Their joint efforts have helped structured a field that remains heterogeneous depending on geographical context and have facilitated the development of more cohesive and cooperative care models. Their participation will be key in the preparation of this monograph, providing expertise, international perspective, and scientific rigor.
This chapter, jointly coordinated by the SEMICYUC Working Group on Hematology, Hemotherapy, and Oncologic Critical Care and by the Oncologic Critical Care Research Network (ONCCC-R-NET),14 aims to provide a structured analysis of the foundational elements underpinning the consolidation of oncologic critical care as an emerging discipline:
- 1
The clinical context, marked by a historic paradigm shift.
- 2
Globalization, expressed through the international expansion of the field and collaborative networks.
- 3
The strategic reasons that justify the growing involvement of Intensive Care Medicine.
- 4
The sense of opportunity derived from the scientific, institutional, and organizational maturity now achieved.
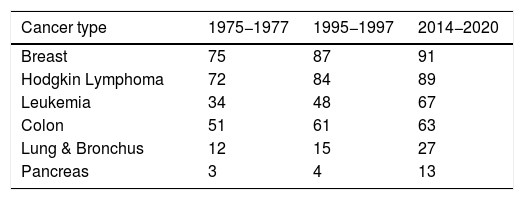
The group of diseases known as cancer is the second leading cause of death around the globe with an estimated death toll above 9.5 million lives in 2018.15,16 The overall risk of developing some form of cancer is 20.2% (22.4% men and 18.2% women); in 2022, there were above 20 million new patients diagnosed with a malignancy (excluding non-melanoma skin cancers).15–17 Even before the explosion of immunotherapies approved in the past 15 years, outcomes have been steadily improving (Table 1). Nevertheless, in spite the efforts of organizations such as the World Health Organization (WHO), the burden of cancer continues growing and it is predicted to reach a 77% increase with more than 35 million new cases by 2050.15,17
Trends in 5-year Survival Rates in the USA 1975 to 2020.
| Cancer type | 1975−1977 | 1995−1997 | 2014−2020 |
|---|---|---|---|
| Breast | 75 | 87 | 91 |
| Hodgkin Lymphoma | 72 | 84 | 89 |
| Leukemia | 34 | 48 | 67 |
| Colon | 51 | 61 | 63 |
| Lung & Bronchus | 12 | 15 | 27 |
| Pancreas | 3 | 4 | 13 |
- The table includes all races and ethnicities.
- The table provides rates that are age adjusted for normal life expectancy.
- These statistics are based on cases diagnosed in the Surveillance, Epidemiology, and End Results (SEER) 9 areas for 1975–1977 and 1995–1997, and in SEER 22 areas for 2014–2020; all cases were followed through 2021.
About 5 to 10% of these patients will suffer adverse events that will lead to ICU admission within two years of diagnosis.18,19 In a large longitudinal study spanning 20 years, the authors reported a 12.9% ICU utilization with an overall ICU mortality of 16.2%.20 In some studies, the proportion of surgical cancer patients admitted to the ICUs is larger.21 However, a significant decrease in the admission rates of the surgical patients has been reported, probably in part associated with the introduction of enhanced recovery after surgery (ERAS) programs.19,21 In a 2015 population-based study of 2.4 million habitants, the overall ICU mortality was reported to be 14.1% (95% CI, 13.3%-15%) and hospital mortality 24.6% (95% CI, 23.5%-25.7%).19 However, mortality rates vary depending on type of admission (e.g., emergent versus elective), type of patients (e.g., surgical versus medical), cancer type and stage (e.g., relapsed/refractory hematological disease), reason for ICU admission (e.g., septic shock versus a treatment-related toxicity), and other factors.
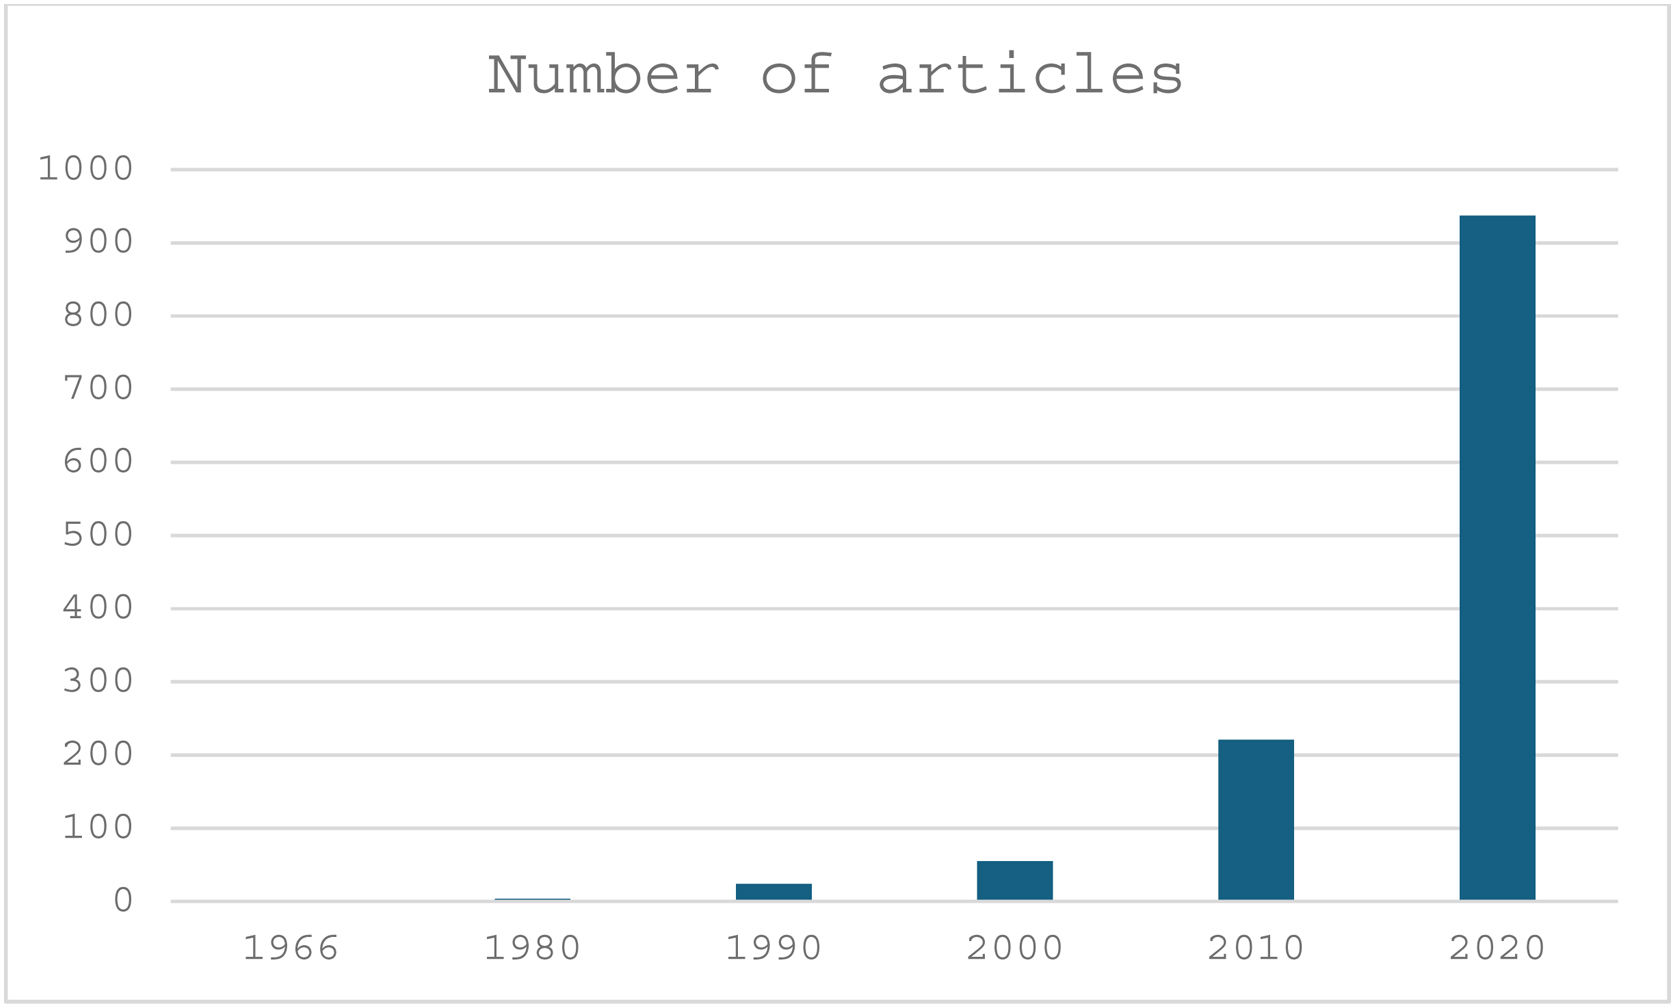
There has been a significant increase in awareness of this patient population previously excluded in critical care research and therefore only able to extrapolate their management from guidelines developed for noncancer or immunocompetent patients.22 A PubMed search for publications involving cancer patients in the ICU returns zero manuscripts in 1966; by 1980, this number had increased to four. Since 2020, however, there has been an exponential growth, reaching a peak in 2021 with 1093 publications using these terms (Fig. 1).
Cancer patients are electively hospitalized to have surgery, receive chemotherapy, and have a stem cell transplant. However, they frequently present to the emergency room and are admitted for a considerable number of different reasons. In the USA, over 4% of the emergency room visits have a cancer related diagnosis and 60% of those admitted have an infectious of cardiopulmonary problem compared to the rest of the population.23 In general, their admission rates are also 3–4 times higher, and the most significant cause is pneumonia.24
In the past 10 years, the access of cancer patients to the ICU has also changed. The prioritization systems have moved critically ill patients from below non-cancer patients admitted just for monitoring (or priority 3) to above them (priority 2, below critically ill patients without cancer).25 The most frequent reasons for ICU admission of this population are respiratory failure, sepsis/shock, acute renal failure, encephalopathy (e.g., stupor, comatose state), gastrointestinal bleeding, and other.26 Surgical cancer patients are mostly admitted for post-operative mechanical ventilation, management of intra-operative complications, or just post-operative monitoring. However, the range of pathologies among the medical patients is very broad and includes the above, but also emergent management of hyperleukocytosis with tumor lysis syndrome, intracranial bleeding associated with severe thrombocytopenia, cytokine release syndrome (CRS), immune effector cell-associated neurotoxicity syndrome (ICANS), immunotherapy-related adverse events (IRAEs) such as pneumonitis, colitis, myocarditis-myositis-myasthenia gravis (triple M syndrome), and many more. As a result of this wide range of pathologies, the percentage of cancer patients in the ICU has increased to be between 15% and 25%.21,27 However, these trends are heterogeneous depending on the region, ICU specialty, and type of patients that each institution manages (e.g., a tertiary trauma center would have a larger proportion of surgical and trauma patients, a center with multiple specialized ICUs could report lower rates).19,21
In the past 15 years, immunotherapy has revolutionized cancer management. In 2016–2017, the American Society of Clinical Oncology named immunotherapy the “Cancer Advance of the Year” and in 2018, Drs. James Allison and Tasuku Honjo received the Nobel Prize for their work in the field.28 As noted above, the recent therapeutic advances in cancer have come with a price.29 However, these patients now benefit from therapies that were not available to them previously due to the stigma of “futility” and the significant improvements made in the management of respiratory failure and sepsis.25,28,30–32 Some examples include early ICU admission, better resuscitation and sepsis protocols, increased compliance with antimicrobial initiation, improved nursing care that included simple head of the bed elevation and frequent oral care among others have helped to improve the outcomes of these patients. Multiple reports of improving outcomes over time and education have helped to ameliorate the mentality associated to futile care for this patient population.33,34
The pattern of admissions and outcomes has further changed. Previously inexistent, admissions to the ICU for complications of chimeric antigen receptor (CAR)-T cell therapy have been associated with excellent results. A multicenter study by Gutierrez et al. showed that 66.7% of the patients had grade 3–4 toxicity after therapy with axicabtagene ciloleucel (also known by its brand name Yescarta) at the time of ICU admission.35 These patients were admitted for a wide range of reasons including ICANS (64%) and CRS (15.2%). While in the ICU, seizures were reported in 20.2%, status epilepticus 5.7%, motor deficits 12.4%, and cerebral edema 7.9%. Patients required vasopressors 18.1%, 10.5% required invasive mechanical ventilation; however, the overall ICU mortality was only 8.6%.
Complication rates associated with immune check point inhibitors (ICI) therapy are also high and frequent reason of ICU admission. Therapy with PD1/PD-L1 is associated with up to 85% grade 1–2 adverse events and grades 3 and 4 up to 27%.36,37 The complication rate is even higher with the combination of PD1/PD-L1 and CTLA4 with up to 95% grades 1–2 and 55% in grades 3–4. In a systematic review and meta-analysis, 14% of the patients developed at least one grade 3 or above adverse event with pneumonitis as the main cause of death among them with 28% followed by sepsis in 8.5% of the cases.38
ICU mortality is usually associated with the severity of illness rather than the underlying cancer or neutropenia26; however, long-term mortality is worse when compared to similar non-cancer survivors.39,40 One year survival for solid tumor patients discharged alive from ICU has been recently reported to be 29.3%.41 However, those that required mechanical ventilation or renal replacement therapy had an ICU survival of only 37 days and 23 days respectively. The short-term outcomes of patients with multi-organ failure, ARDS, septic shock, or acute renal failure requiring continuous renal replacement therapy still remain poor.42–44
Advances in the management of the main causes of ICU admission and mortality have helped improving the clinical outcomes of critically cancer patients. The introduction of non-invasive ventilation and high-flow oxygen therapy via nasal cannula has led to a more conservative approach reducing the need for intubation and invasive mechanical ventilation, thus decreasing aspiration pneumonia/ventilator-associated pneumonia and hemodynamic impairments.45,46 These interventions as well as the guidelines to manage sepsis, the spread of quality improvement initiatives by the Institute of Healthcare Improvement, early diagnostic tools to rapidly identify allowed to tailor antibiotic therapy in sepsis, improved oral care, aspiration precautions, newer technologies facilitating earlier detection of the culprit organisms, earlier ICU admission, and many more have all contributed to decrease mortality.33,34,47–49
GlobalizationAcross the United States, Canada, the European Union, and countries including Brazil, Japan, and Australia, we have witnessed an increasing development of oncologic-specialized care within intensive care units, particularly in cancer-specialized centers. Worldwide, growing evidence supports the benefit of the specialized care for cancer patients in the ICUs. The ORCHESTRA study in Brazil demonstrated better outcomes for oncologic patients admitted to specialized units, albeit with increased severity upon admission.50 The European union has made significant advances in promoting awareness among physicians on the importance to critical care intervention in the oncologic population. Transnational initiatives such as the Intensive Care in Hematologic and Oncologic Patients (iCHOP) aims to improve critical care for patients with blood and solid cancer disorders. These initiatives, with the support and involvement of intensive care societies gain ground for the development of standardization policies and consensus statements.51
In the United States, institutions, especially those well-recognized or specialized in cancer care such as MD Anderson Cancer Center (MDACC) and Memorial-Sloan Kettering (MSK), have led in the development of dedicated intensive care units to cancer patients. Nonetheless for most, oncologic critical care is a new concept that had not been addressed in the classic critical care textbooks or common literature. It was not until recently that a comprehensive textbook addressed this educational gap.52 There are also gaps in professional recognition. Specialty training in oncology critical care has started to be offered in some institutions such as MDACC and MSK but it lacks recognition by credentialing agencies or standard structural guidance.
Worldwide this situation is even more concerning. In Latin-America, as an example, it was not until the Manta agreement in 2012, where ONCC-R-NET was created, that some of the national intensive and critical care societies started to include oncologic chapters to recognize the increasing demand for this specialty care. Since then, some slow progression has been seen, with transnational efforts promoted by the Pan-American and Iberic Federation of Critical Care Societies (FEPIMCTI) and its Expert Committees generating some recommendations and two recent textbooks.53,54
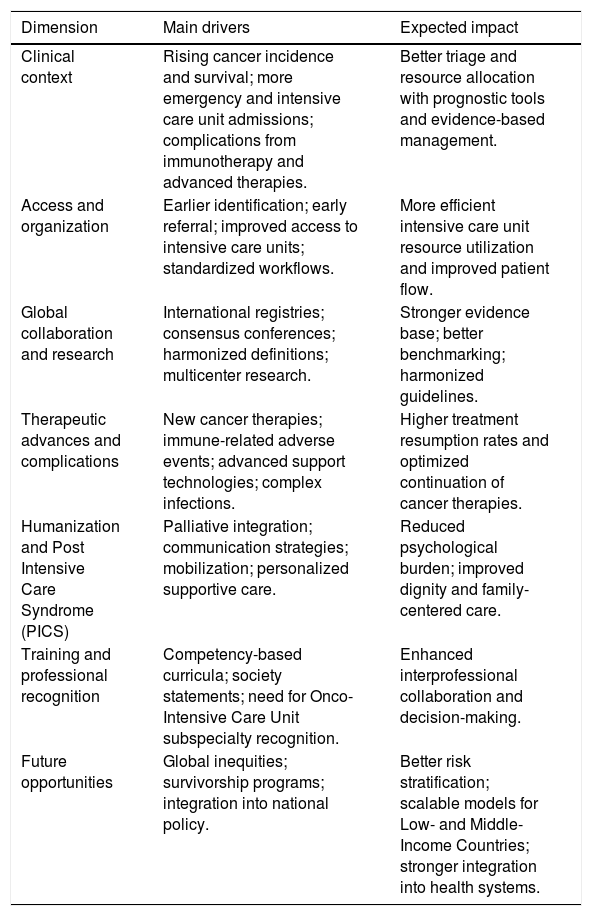
The World Federation of Intensive and Critical Care (WFICC), in close collaboration with ONCCC-R-NET and the recently created Global Society of Oncologic Critical Care (GSOCC), has engaged in a very active campaign worldwide for the promotion and increasing awareness of the need for oncologic critical care. In addition to educational activities, such as webinars, and specialty track in the future world congresses, WFICC has declared oncologic critical care as one of its pillars in the future development of intensive and critical care (WFICC 2025-2030 Strategic Plan – in press). Furthermore, the master collaborative agreement between WFICC and the World Health Organization (WHO) calls for the expansion of this project, and other initiatives to spare regions of the world, where there is even a bigger gap regarding the critical care of cancer patients. Collaboration among the many international groups and networks currently involved in this field has become increasingly essential for developing standards, guidelines, and research and educational initiatives that advance global efforts to enhance the quality and consistency of critical care delivered to cancer patients. Some of the key dimensions in the consolidation of oncologic critical care as a discipline is enumerated in Table 2.
Key dimensions in the consolidation of oncologic intensive care as a discipline.
| Dimension | Main drivers | Expected impact |
|---|---|---|
| Clinical context | Rising cancer incidence and survival; more emergency and intensive care unit admissions; complications from immunotherapy and advanced therapies. | Better triage and resource allocation with prognostic tools and evidence-based management. |
| Access and organization | Earlier identification; early referral; improved access to intensive care units; standardized workflows. | More efficient intensive care unit resource utilization and improved patient flow. |
| Global collaboration and research | International registries; consensus conferences; harmonized definitions; multicenter research. | Stronger evidence base; better benchmarking; harmonized guidelines. |
| Therapeutic advances and complications | New cancer therapies; immune-related adverse events; advanced support technologies; complex infections. | Higher treatment resumption rates and optimized continuation of cancer therapies. |
| Humanization and Post Intensive Care Syndrome (PICS) | Palliative integration; communication strategies; mobilization; personalized supportive care. | Reduced psychological burden; improved dignity and family-centered care. |
| Training and professional recognition | Competency-based curricula; society statements; need for Onco-Intensive Care Unit subspecialty recognition. | Enhanced interprofessional collaboration and decision-making. |
| Future opportunities | Global inequities; survivorship programs; integration into national policy. | Better risk stratification; scalable models for Low- and Middle-Income Countries; stronger integration into health systems. |
Based on the epidemiologic trends, the strategic reasons for the expansion of oncologic critical care education and services are obvious.15–17 Cancer patients are occupying ICU beds with increasing frequency. As noted previously, these patients experience a wide range of complications arising from their underlying malignancies, concomitant comorbidities, and the therapies they receive. Intensivists, natural leaders of the critical care team, are then confronted with life-threatening organ dysfunctions affecting critically ill cancer patients and the added difficulties carried by the different views regarding life expectancy and support requirements for these types of patients. Oncologists more often focus on the cancer characteristics and future therapeutic options, whereas intensivists focus on multiple organ failure when weighing in on the same decisions.55 This complexity creates challenging situations, many of them not covered in our academic curriculums.
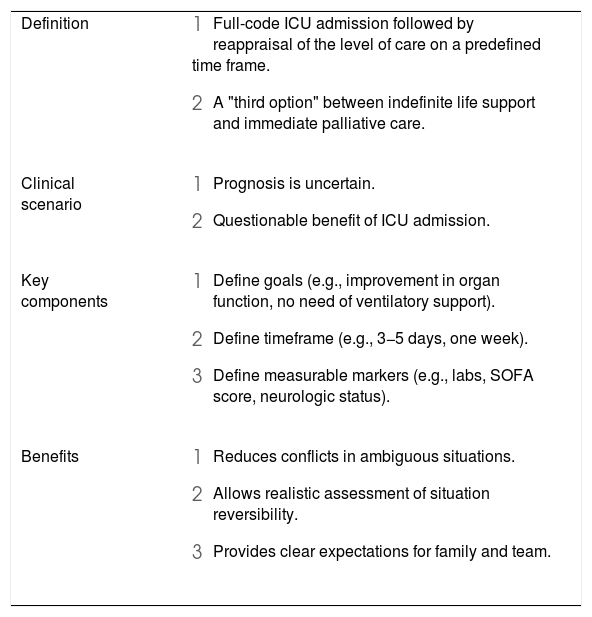
Scheduled meetings between oncologists and intensivists may reduce possible conflicts regarding the critical care of patients with cancer and is associated with a lower mortality.56 Protocols should be implemented and updated in each hospital, according to patient’s case mix and local peculiarities. The so-called “ICU-trial” is the recommended approach in uncertain prognosis or when not a unanimous decision can be reached by intensivists and oncologists/hematologists (Table 3). It requires careful monitoring to avoid prolonged interventions with valueless benefit.57 Sometimes it may be emotionally difficult to stop, especially for oncologists/hematologists that have treated the patient for months or years. Obviously, care teams must respect patient’s values and previous statements.
Definitions and components of the “ICU Trial”.
| Definition |
|
| Clinical scenario |
|
| Key components |
|
| Benefits |
|
Beyond the contribution of early diagnosis and supportive care, the prolonged survival in cancer is due in great part to a new generation of targeted cancer treatments. Early admission of critical oncological patients improves their prognosis and has been identified as an independent factor associated with higher survival rates.58,59 In addition, cancer patients frequently have previous comorbidities that requires specialized skills by the intensivist and a multidisciplinary approach. New therapies not only lead to greater life expectancy, but also open new challenges in the management of toxicities and complications. Severe immunosuppression characterizes these patients and makes them vulnerable to invasive infections including opportunistic pathogens.
Intensivists need to increase their knowledge of common critical conditions in cancer patients, such as sepsis or the diagnosis and management of opportunistic infections that frequently affect these patients, as well as cancer-specific issues like tumor lysis syndrome, leukostasis, or severe toxicities from treatments like chemotherapy or immunotherapy. This learning must be included in the residents' training program, be continuously updated, and reinforced to increase this expertise. New immunotherapies are increasingly used by oncologists and hematologists, and their toxicities can lead to rapid deterioration that is unfamiliar to traditional critical care. ICU staff need structured training to recognize and manage critical care support for immune-related severe side- events.60 In this scenario, research is absolutely necessary, and international collaborative platforms created to connect oncologic critical care researchers facilitate joined work aimed to improve the prognosis of critically ill cancer patients.
Sense of opportunityCritical oncology has evolved almost exponentially over the past decade, primarily driven by increased patient survival and advances in therapeutic strategies across different stages of disease, and even more markedly by the development of immunotherapy.61 This evolution undoubtedly poses a major challenge for the scientific community, and particularly for Intensive Care Medicine. Patients with cancer constitute a significant and growing proportion of ICU admissions, representing over 15% of all admissions in our setting, albeit with substantial inter-center variability.21,27,62
In this population, prognostic factors, admission criteria, and therapeutic decisions likely differ from those applied to other ICU patients. Consequently, new predictive, organizational, and planning strategies—as well as training in emerging treatments—are required, demanding heightened awareness and multiprofessional collaboration.63–65 There is an urgent need to develop and validate novel predictive models that integrate functional status, tumor characteristics, and treatment response to enhance objectivity in clinical decision-making.66
In this context, collaborative networks, both national and international, must play a pivotal role. Through multicenter studies, global registries, and transnational working groups, it is possible to generate robust and harmonized evidence, overcoming limitations associated with heterogeneous healthcare systems and the relatively low prevalence of certain clinical conditions. Scientific cooperation can not only advance the pathophysiological understanding of critical complications in oncology patients but also provide comparative frameworks for clinical practice guidelines, care protocols, and quality-of-care metrics.
Scientific output will help strengthen the visibility and legitimacy of critical oncology. The systematic publication of methodologically rigorous studies, narrative reviews, and expert consensus statements will contribute to positioning this discipline within the international academic agenda. Such editorial efforts facilitate the rapid dissemination of concepts, therapeutic strategies, and diagnostic tools among professionals from diverse fields, fostering a truly interdisciplinary approach.
Within this process, Intensive Care Medicine professionals must assume a leadership role in both patient care and knowledge generation. In Spain, research efforts are underway in this direction, as reflected in recent publications on the subject.61–67 The current moment therefore represents a strategic opportunity to definitively integrate critical oncology into national and international clinical guidelines, training programs, and health policies designed for the management of complex diseases. Advancing toward a personalized, sustainable, and global discipline requires strengthening specialized training, improving coordination among different specialties and healthcare professionals, and promoting health systems capable of responding to the evolving needs of these patients. The consolidation of critical oncology as an autonomous and structured field is not only possible today, but necessary.
It is evident that, throughout this process, artificial intelligence systems will play a pivotal role in the development of management and sustainability strategies, the construction of predictive models, and the expansion of personalized treatment options. It will be essential to ensure appropriate use of these systems—overcoming ethical challenges and issues of trust—by incorporating adequately trained professionals and generating high-quality shared databases. This already represents a significant challenge for international scientific societies and for society at large.68
ConclusionIn the past 25 years, there has been a progressive shift in perspective and growing awareness regarding the management of critically ill patients with cancer. Intensivists around the world advocating for this population have significantly and positively affected ICU access, education, research, and outcomes of critically ill cancer patients. This article, in conjunction with the others in this issue, represent a deliberate and collaborative commitment to continue facilitating knowledge transfer, promoting the expansion of a dedicated scientific space, and fostering the development of synergies that will further enable progress in this field.
Declarations- •
Regarding this manuscript, the authors do not have any conflict of interest to declare.
- •
No artificial intelligence tools were used to create this manuscript.
- •
The authors declare no conflict of interest.
- •
There is no funding source to declare.
- •
All thew authors contributed equally to the creation of this work in the design, writing, and approval of the final version of the manuscript.



